Impact of viral genetic variation on polyclonal and monoclonal antibodies
Jesse Bloom
Fred Hutch Cancer Center / HHMI
Gilead
September 18, 2026
Two parts to this talk:
1) Sequencing-based neutralization assays measure impact of strain-to-strain variation (example used: influenza virus hemagglutinin)
2) Deep mutational scanning to understand impact of all amino-acid mutations in a single strain background (example used: RSV F)
Sequencing-based neutralization assays (applied to influenza)
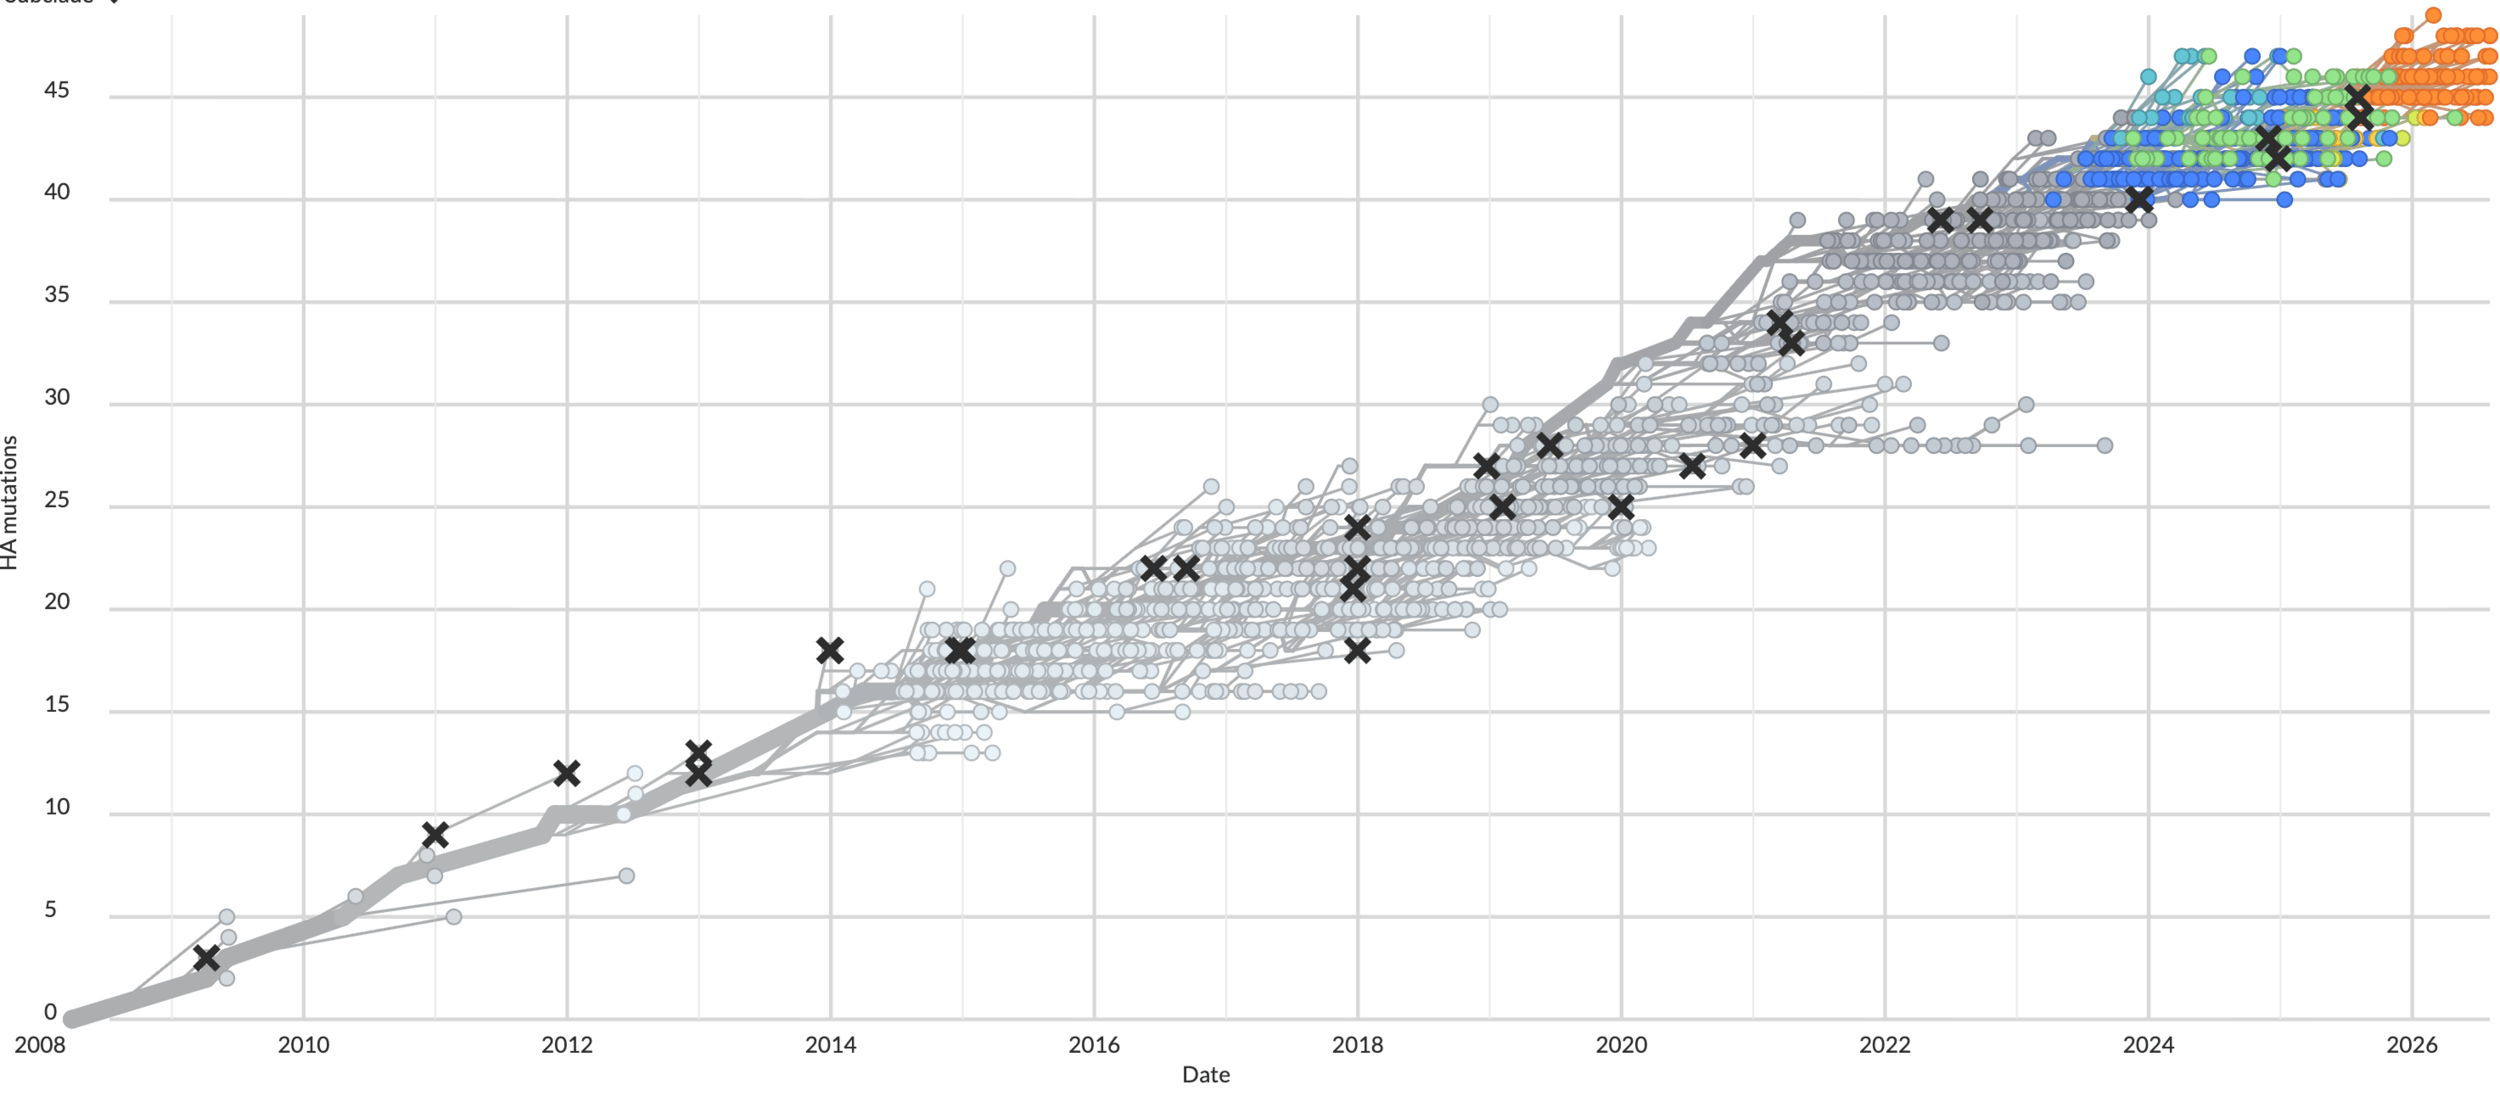
Year
HA amino-acid mutations
Hemagglutinin (HA) of human influenza evolves rapidly
HA of human H3N2 influenza has accumulated >45 mutations over last 18 years. x indicates vaccine strains.
HA evolution fixes mutations in regions targeted by neutralizing antibodies
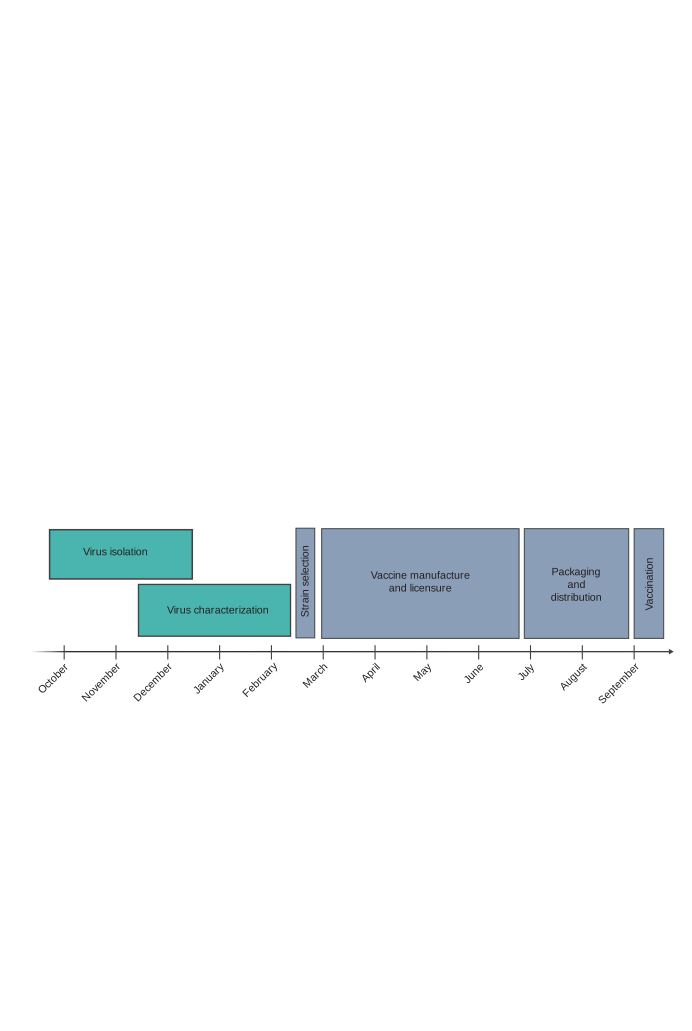
Due to influenza evolution, vaccine updated ~9 months before it will be used each year
In February strains chosen for Northern Hemisphere vaccine administered ~October that year.
In September, strains chosen for Southern Hemisphere vaccine administered the next ~May.
Separate update decisions for H3N2, H1N1, and B strains; not every component changed each time.
Traditional neutralization assays are low throughput (each row measures one serum vs one virus)
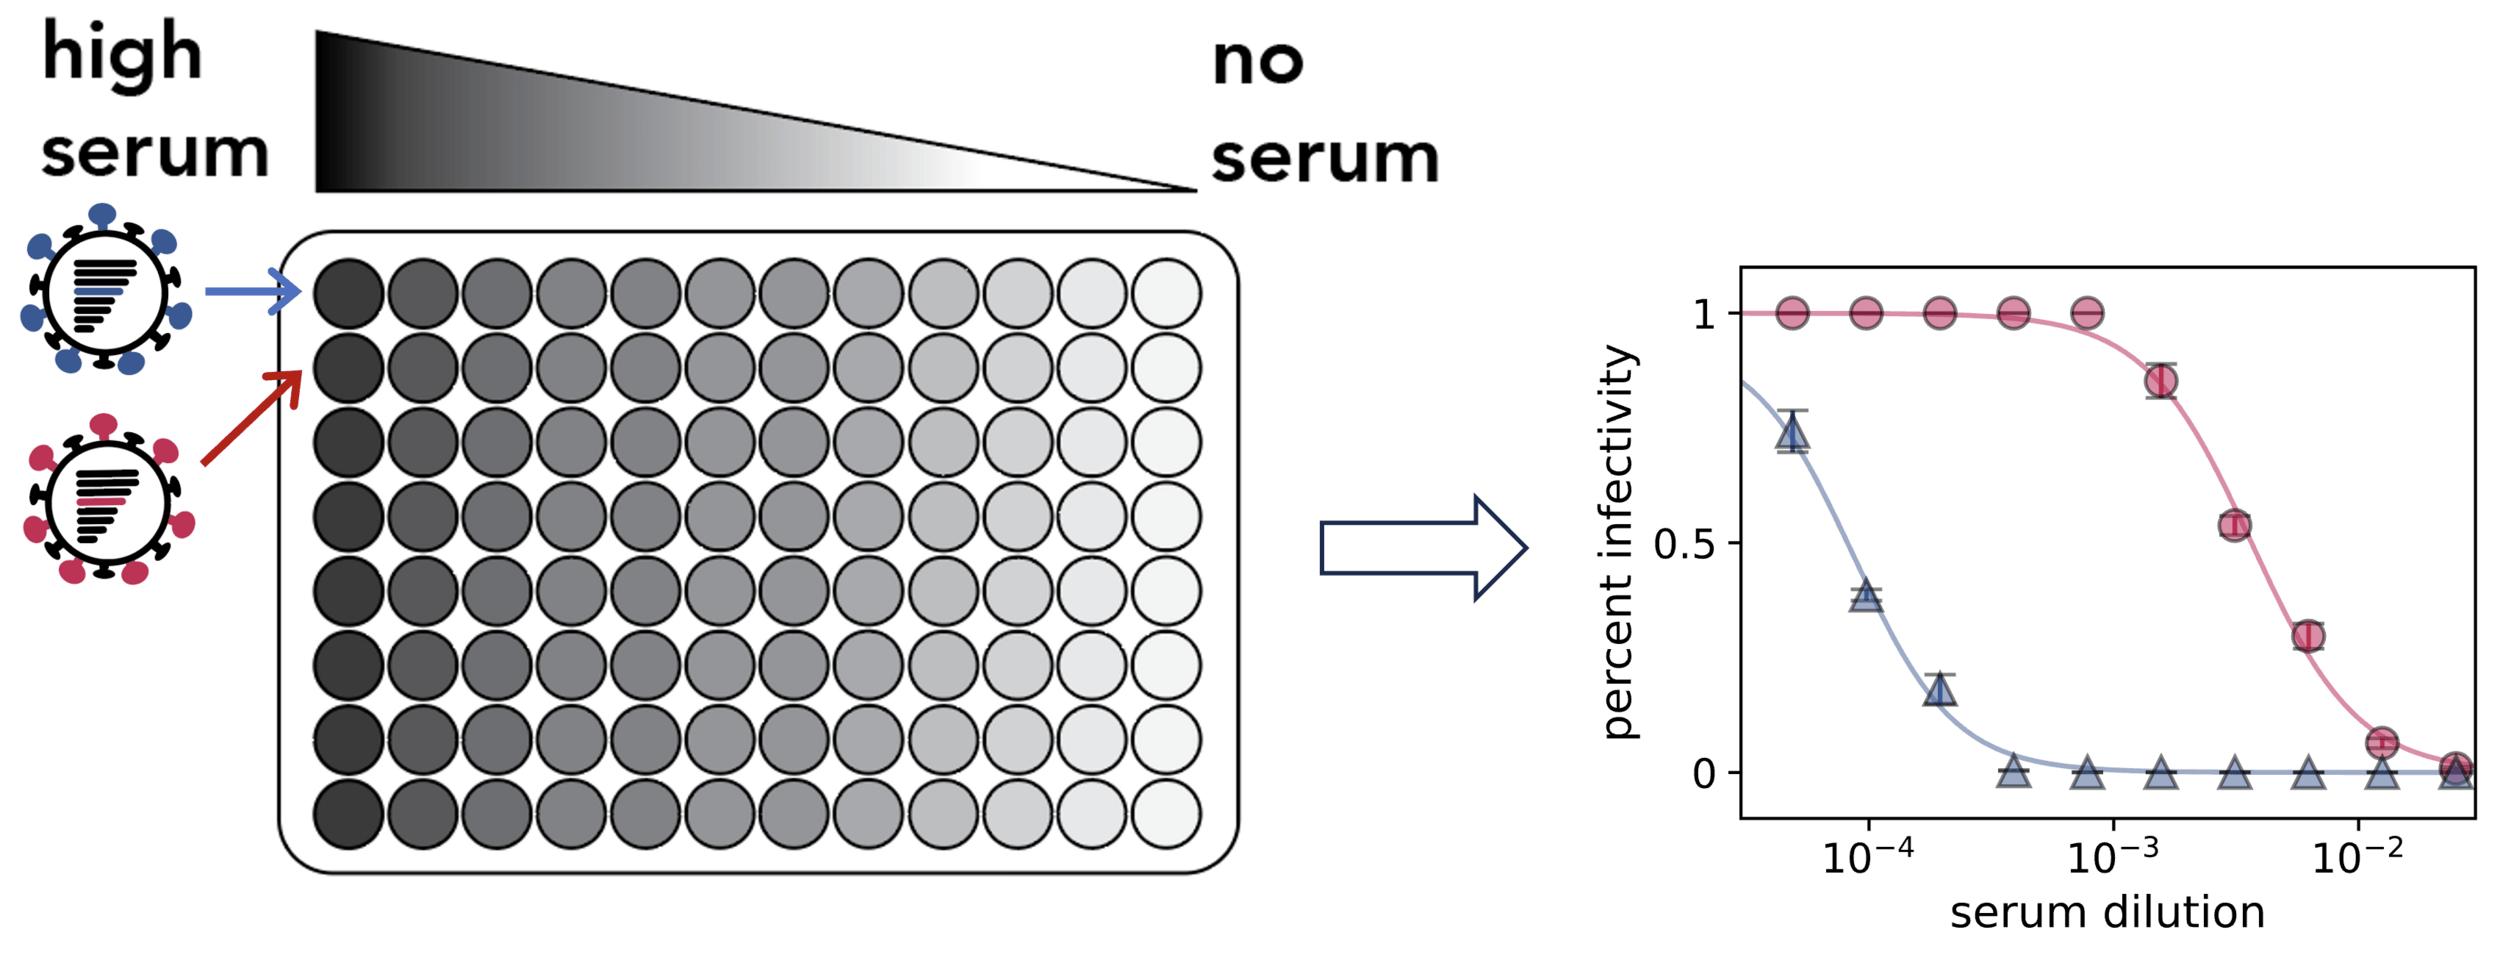
fraction infectivity
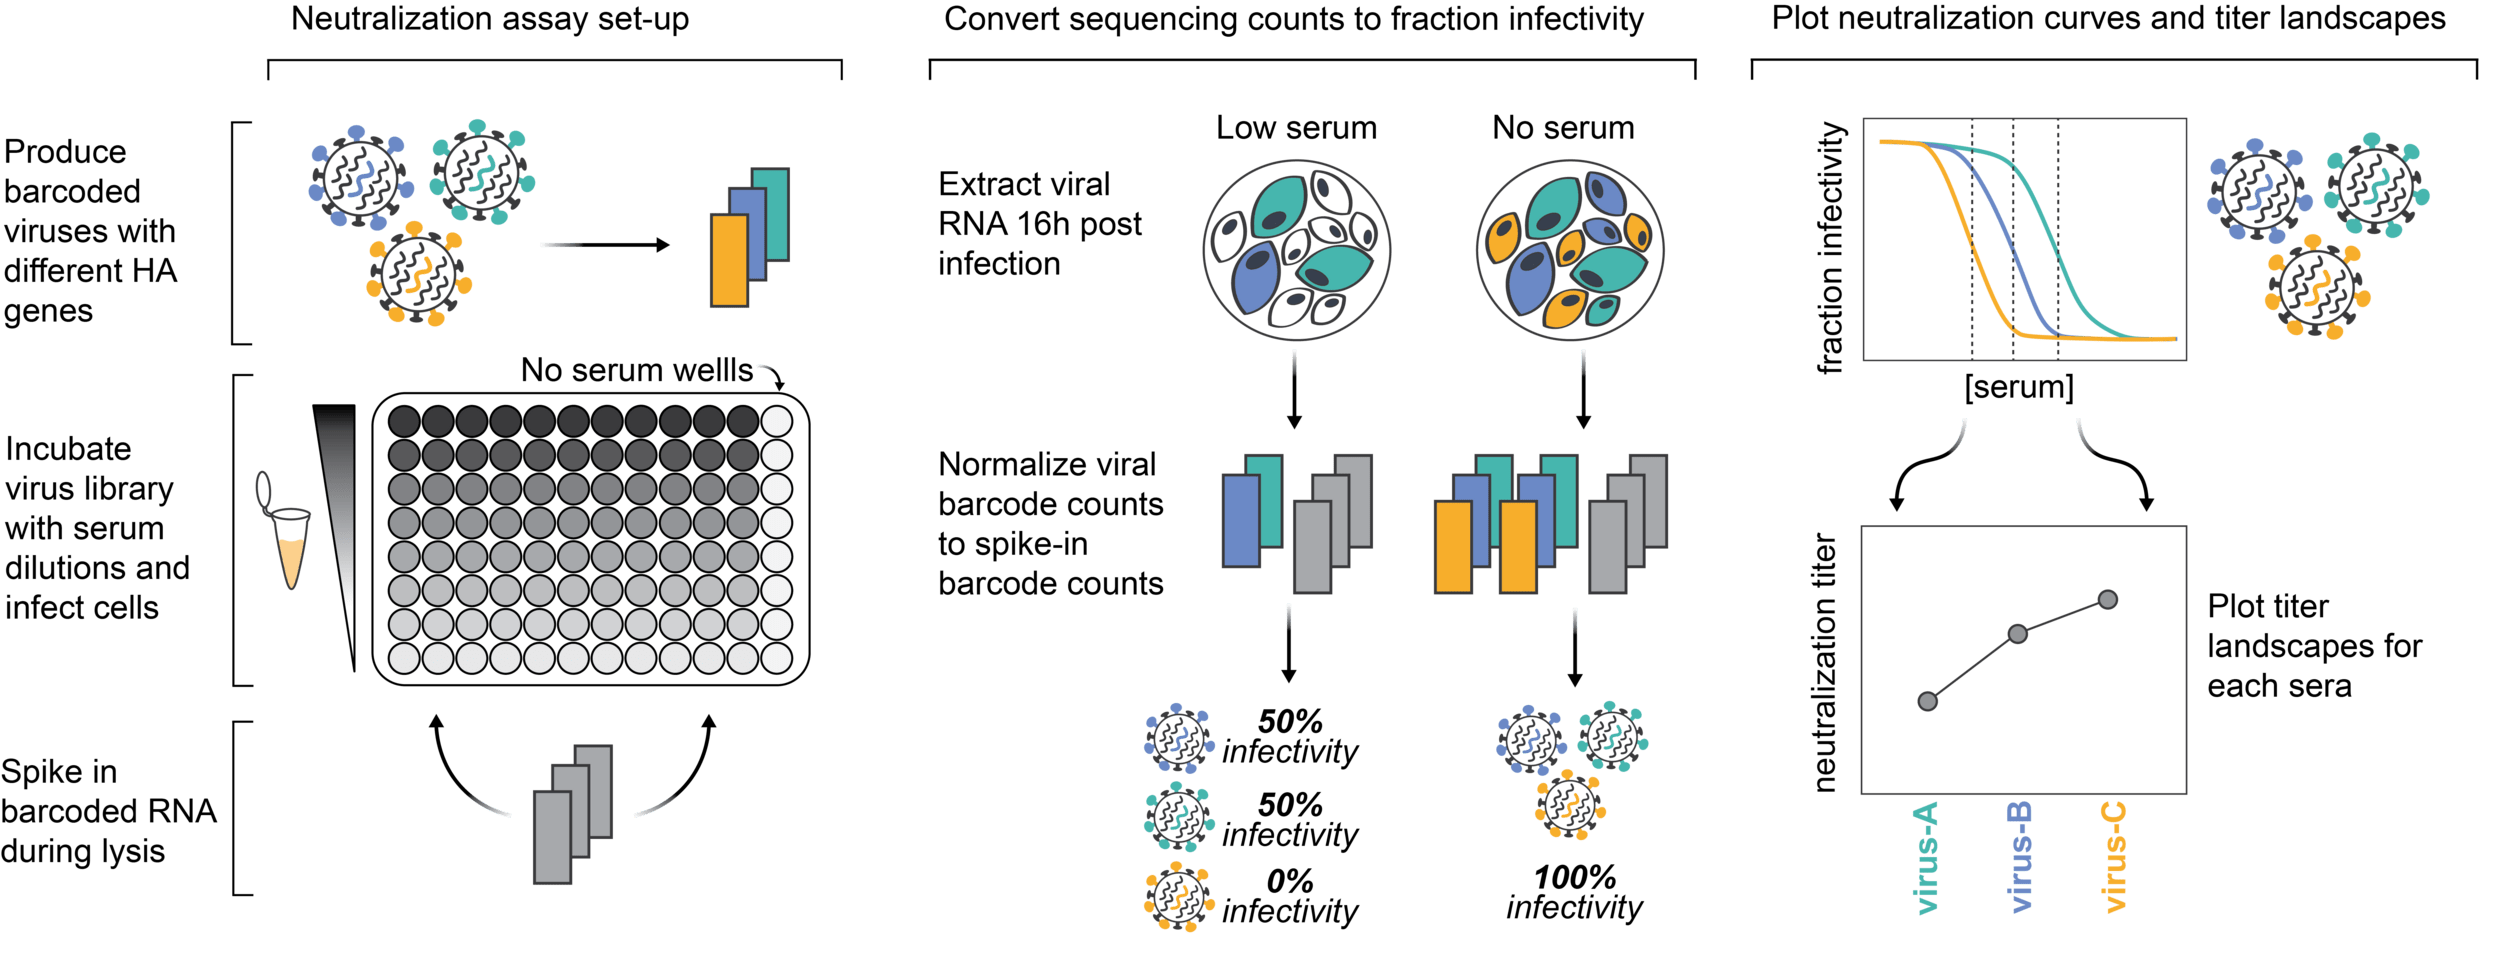
Sequencing-based neutralization assays measure titers to many strains at once
Sequencing-based neutralization assays measure titers to many strains at once
Sequencing-based neutralization assays measure titers to many strains at once
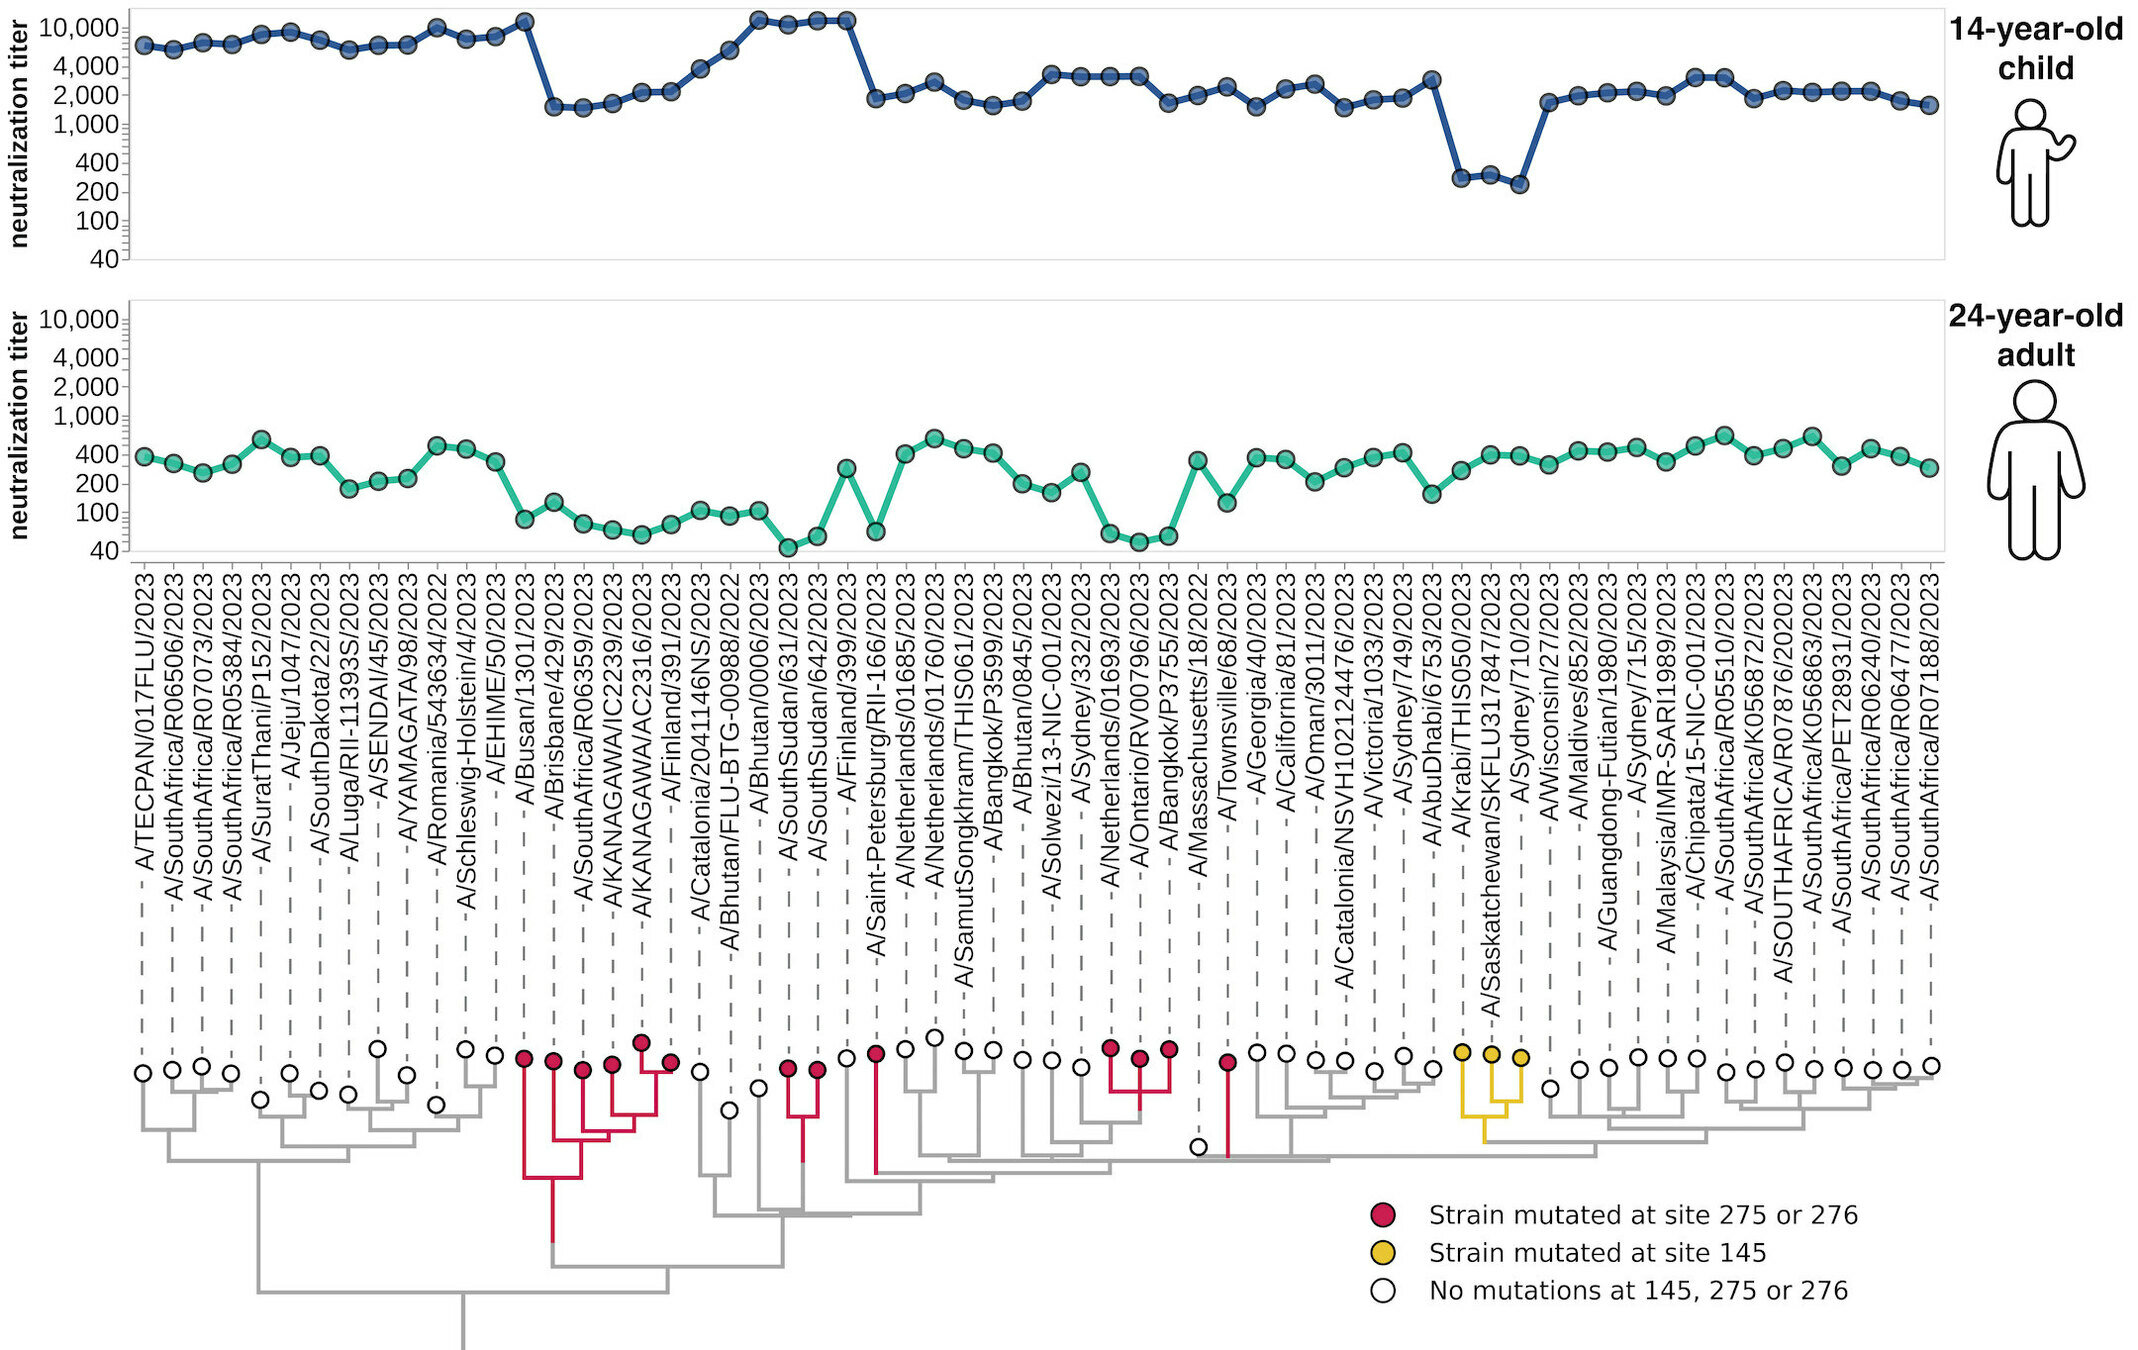
different recent H3N2 viral strains
Measure titers to many strains for each serum
child has low titers to these strains
different recent H3N2 viral strains
Strain-specific titers differ among people
child has low titers to these strains
adult has low titers to these strains
Near real-time measurement of titers to recent strains to inform vaccine choice
All data openly shared as it is collected, so anyone can analyze it to inform vaccine-strain selection and advance public health.
Currently generating data for A/H3N2 and A/H1N1; hope to expand to influenza B.
Data shared so far:
- Aug/Sep 2025: https://github.com/jbloomlab/flu-seqneut-2025; Kikawa et al (2025)
- Jan/Feb 2026: https://github.com/jbloomlab/flu-seqneut-2025to2026; Kikawa et al (2026)
- Aug/Sep 2026: https://github.com/jbloomlab/flu-seqneut-2026; Kikawa et al (2026b)
In May, we chose set of recent seasonal strains
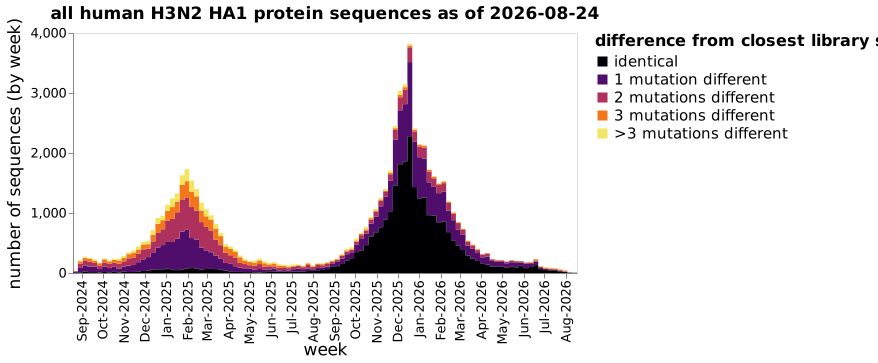
Most recently sequenced human influenza within one HA1 mutation of strain in our set
Most recently sequenced human influenza within one HA1 mutation of strain in our set
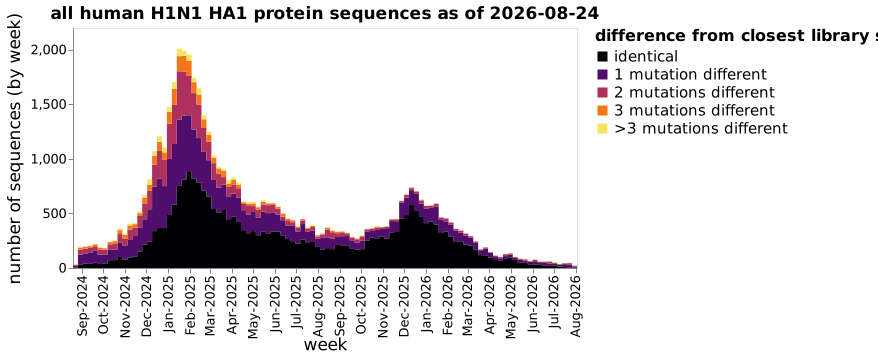
Measured neutralization of 78 H3N2 and 62 H1N1 strains by >300 human sera
Human sera assayed (all collected between April and June of 2026):
- Seattle Children's Hospital: convenience samples
- University of Washington Medical Center: convenience samples
- Creative Testing Solutions / UCSF: samples from blood donors
- Victorian Infectious Diseases Lab (Australia): pre- or post-vaccine samples
H3N2 results
Low titers to some emerging subclade K variants
Lowest titers are to subclade K variants with mutation at sites 222 or 223.
See also:
Sites 222 and 223 are in region of HA not mutated in original subclade K
Mutations at these sites likely erode residual antibodies not already escaped by earlier subclade K mutations; see Liu et al (2026).
H1N1 results
Low titers to D.3.1.1, especially with G155E
Most D.3.1.1 strains have lower titers than current D.3.1 vaccine.
Titers lowest to strains with G155E.
See also:
G155E most affects potent sera from 15-25 yr olds
D.3.1.1 has several mutations relative to D.3.1, with G155E an additional change
Conclusions
Sequencing-based neutralization assays can measure the neutralization of recent strains by current human antibodies in near real time.
These titer measurements are informative about influenza evolution.
We are generalizing sequencing-based neutralization assays to the entry proteins of other viruses.
Deep mutational scanning (applied to RSV F)
Respiratory syncytial virus (RSV) is leading cause of infant hospitalization in USA
In developed world, infants hospitalized with RSV receive supportive care (eg, oxygen, ventilation, fluids) and usually recover (~0.1% in-hospital case-fatality rate)
In developing world where supportive care not available, RSV is a leading cause of infant mortality (~100,000 infant deaths per year)
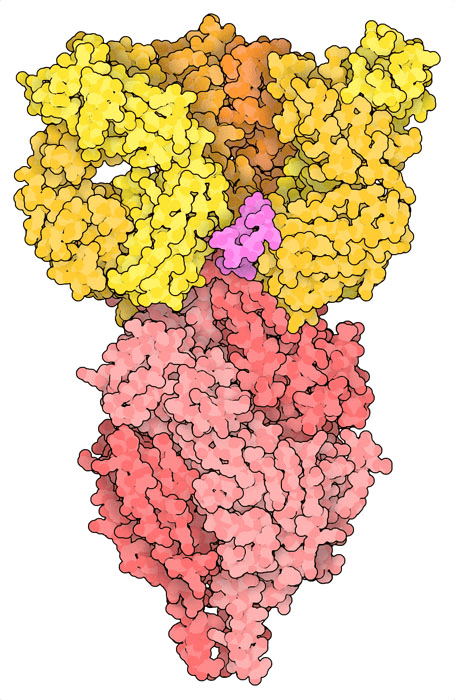
the antibody nirsevimab bound to prefusion F at epitope that includes glycan

Antibodies can bind to RSV F and neutralize viral infection of cells
Brief history of anti-F antibodies for RSV prevention in infants

Palivizumab
Lower potency than subsequent antibodies.
Due in part to cost, recommendation only for infants born <29 weeks gestational age or <32 weeks with chronic lung disease
Neutralization curves from Simonich et al (2025)

Suptavumab
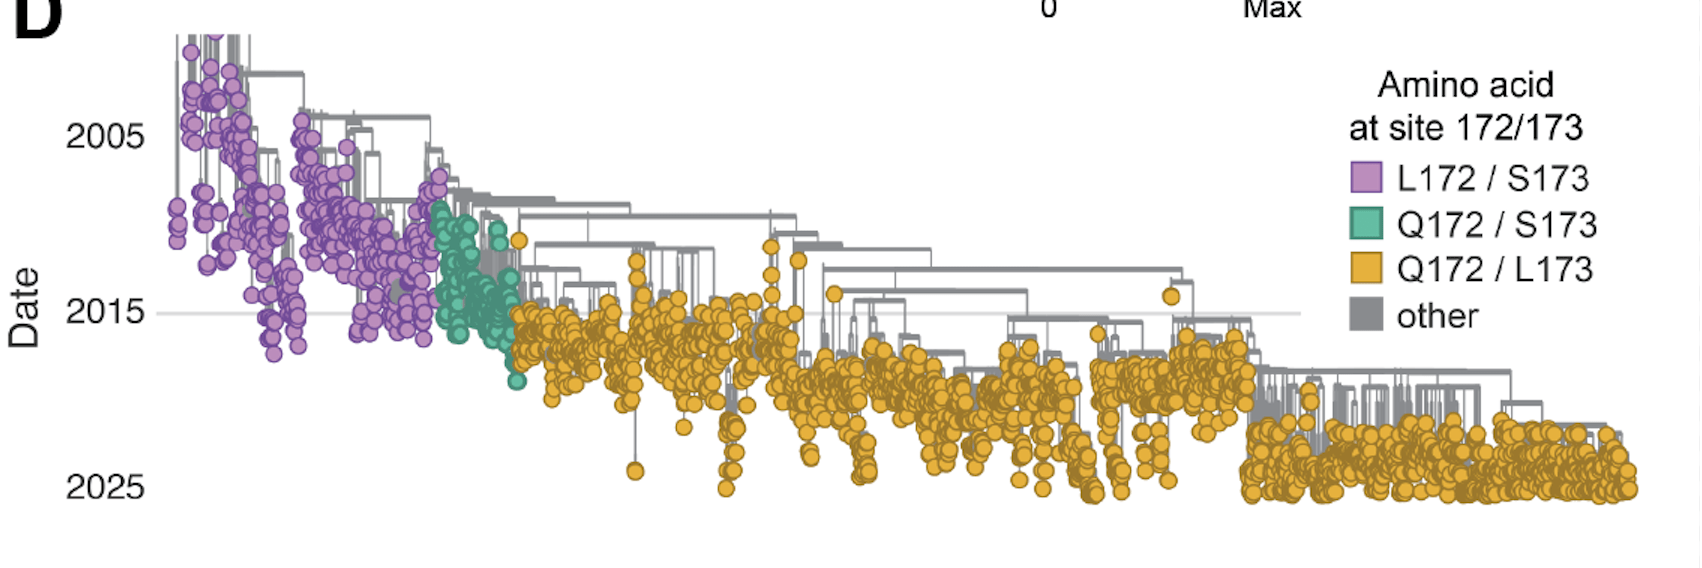
Much more potent against some strains than palivizumab.
Failed Phase 3 clinical trial from 2015-2017 due to lack of efficacy against subtype B; coincided with evolution of new variants with mutations at F sites 172 and 173.
Neutralization curves from Simonich et al (2025)

High potency and extended half life.
Recommended in United States in 2023 for all infants <8 months old entering their first RSV season.
~80% effectiveness in preventing RSV hospitalization.
Nirsevimab
Neutralization curves from Simonich et al (2025)

Clesrovimab
High potency and extended half life similar to nirsevimab but targets different region of F.
Approved in United States in 2025.
Neutralization curves from Simonich et al (2025)

The clinical antibody nirsevimab neutralizes most RSV strains
plotted data from Simonich et al (2025)

Resistant strains have been identified in clinical and lab-passaging studies, plotted data from Simonich et al (2025)
But some (currently rare) natural RSV strains escape nirsevimab neutralization
The mysterious subtype-dependence of nirsevimab-escape mutations
Two subtypes of RSV: A & B. Their F proteins have ~90% sequence identity & similar structures
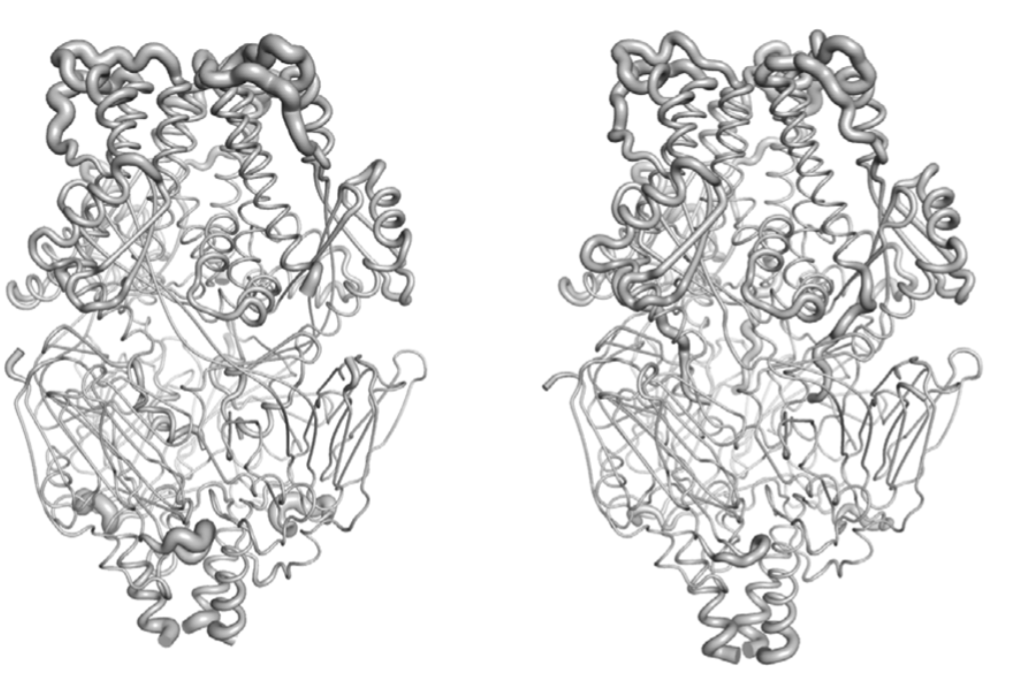
RSV B F structure
RSV A F structure
The structures have a RMSD deviation of only 1.8 angstroms.
Nirsevimab IgG has similar neutralization of RSV A and RSV B
plotted data from Simonich et al (2025)

But resistance is more common for RSV B than A in nirsevimab-treated infants
| study | resistance in RSV-A | resistance in RSV-B |
|---|---|---|
| Fourati et al (2025a) | 2/195 = 1% | 23/184 = 13% |
| Fourati et al (2025b) | 0/236 = 0% | 2/24 = 8% |
| Ahani et al (2023) | 0/11 = 0% | 2/14 = 14% |
Rates of resistance to nirsevimab neutralization in RSV breakthrough infections of infants who received nirsevimab.
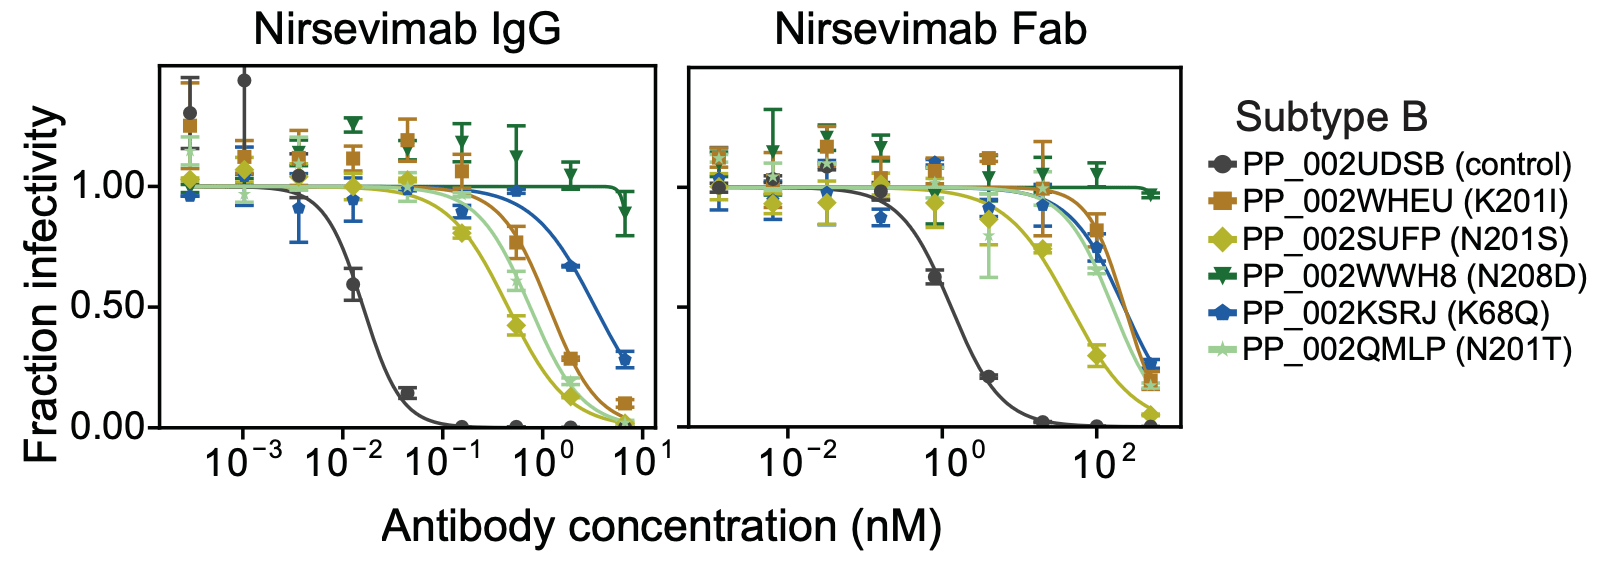
Some F mutations reduce nirsevimab neutralization of subtype B but not A

Why is RSV B more prone to nirsevimab resistance despite IgG neutralizing both subtypes similarly?
IgG antibodies are bivalent, with two connected Fabs
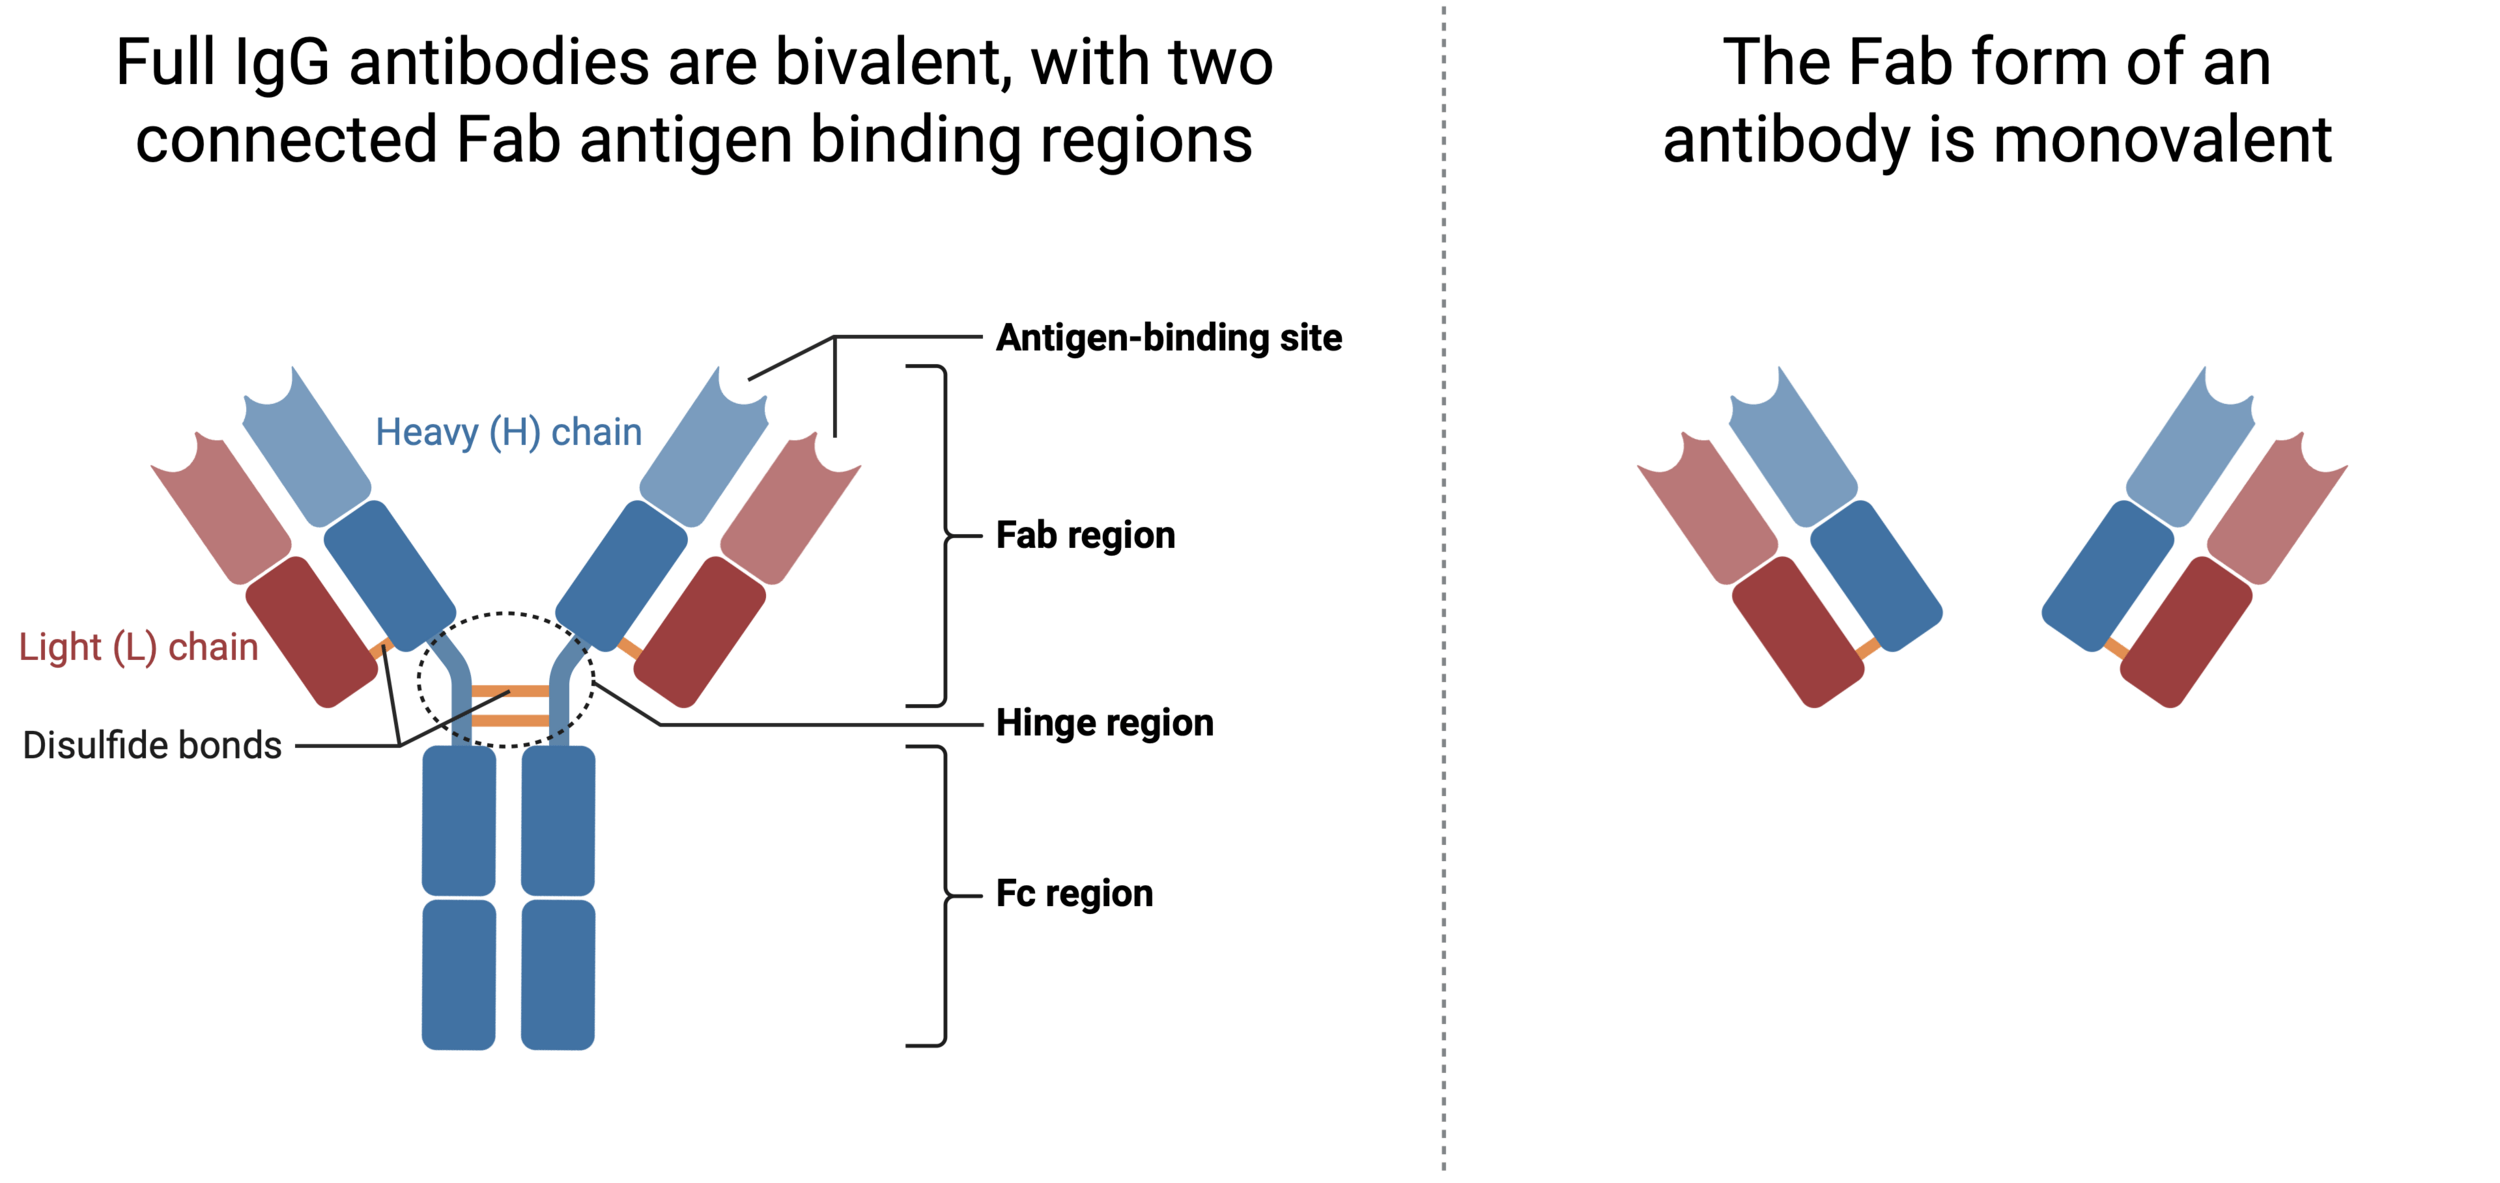
Apparent affinity (avidity) of bivalent IgG can be very high
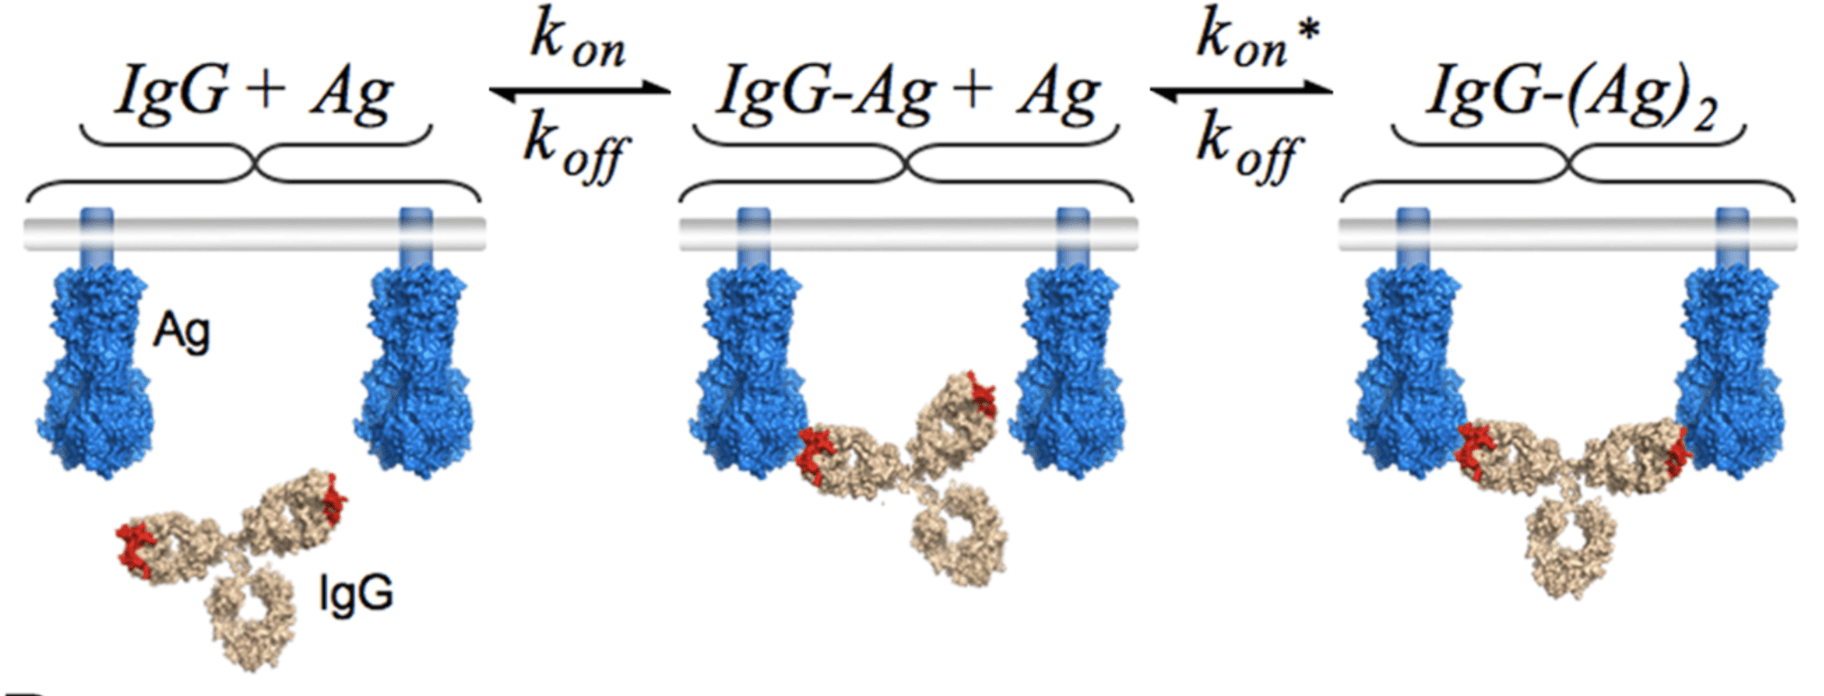
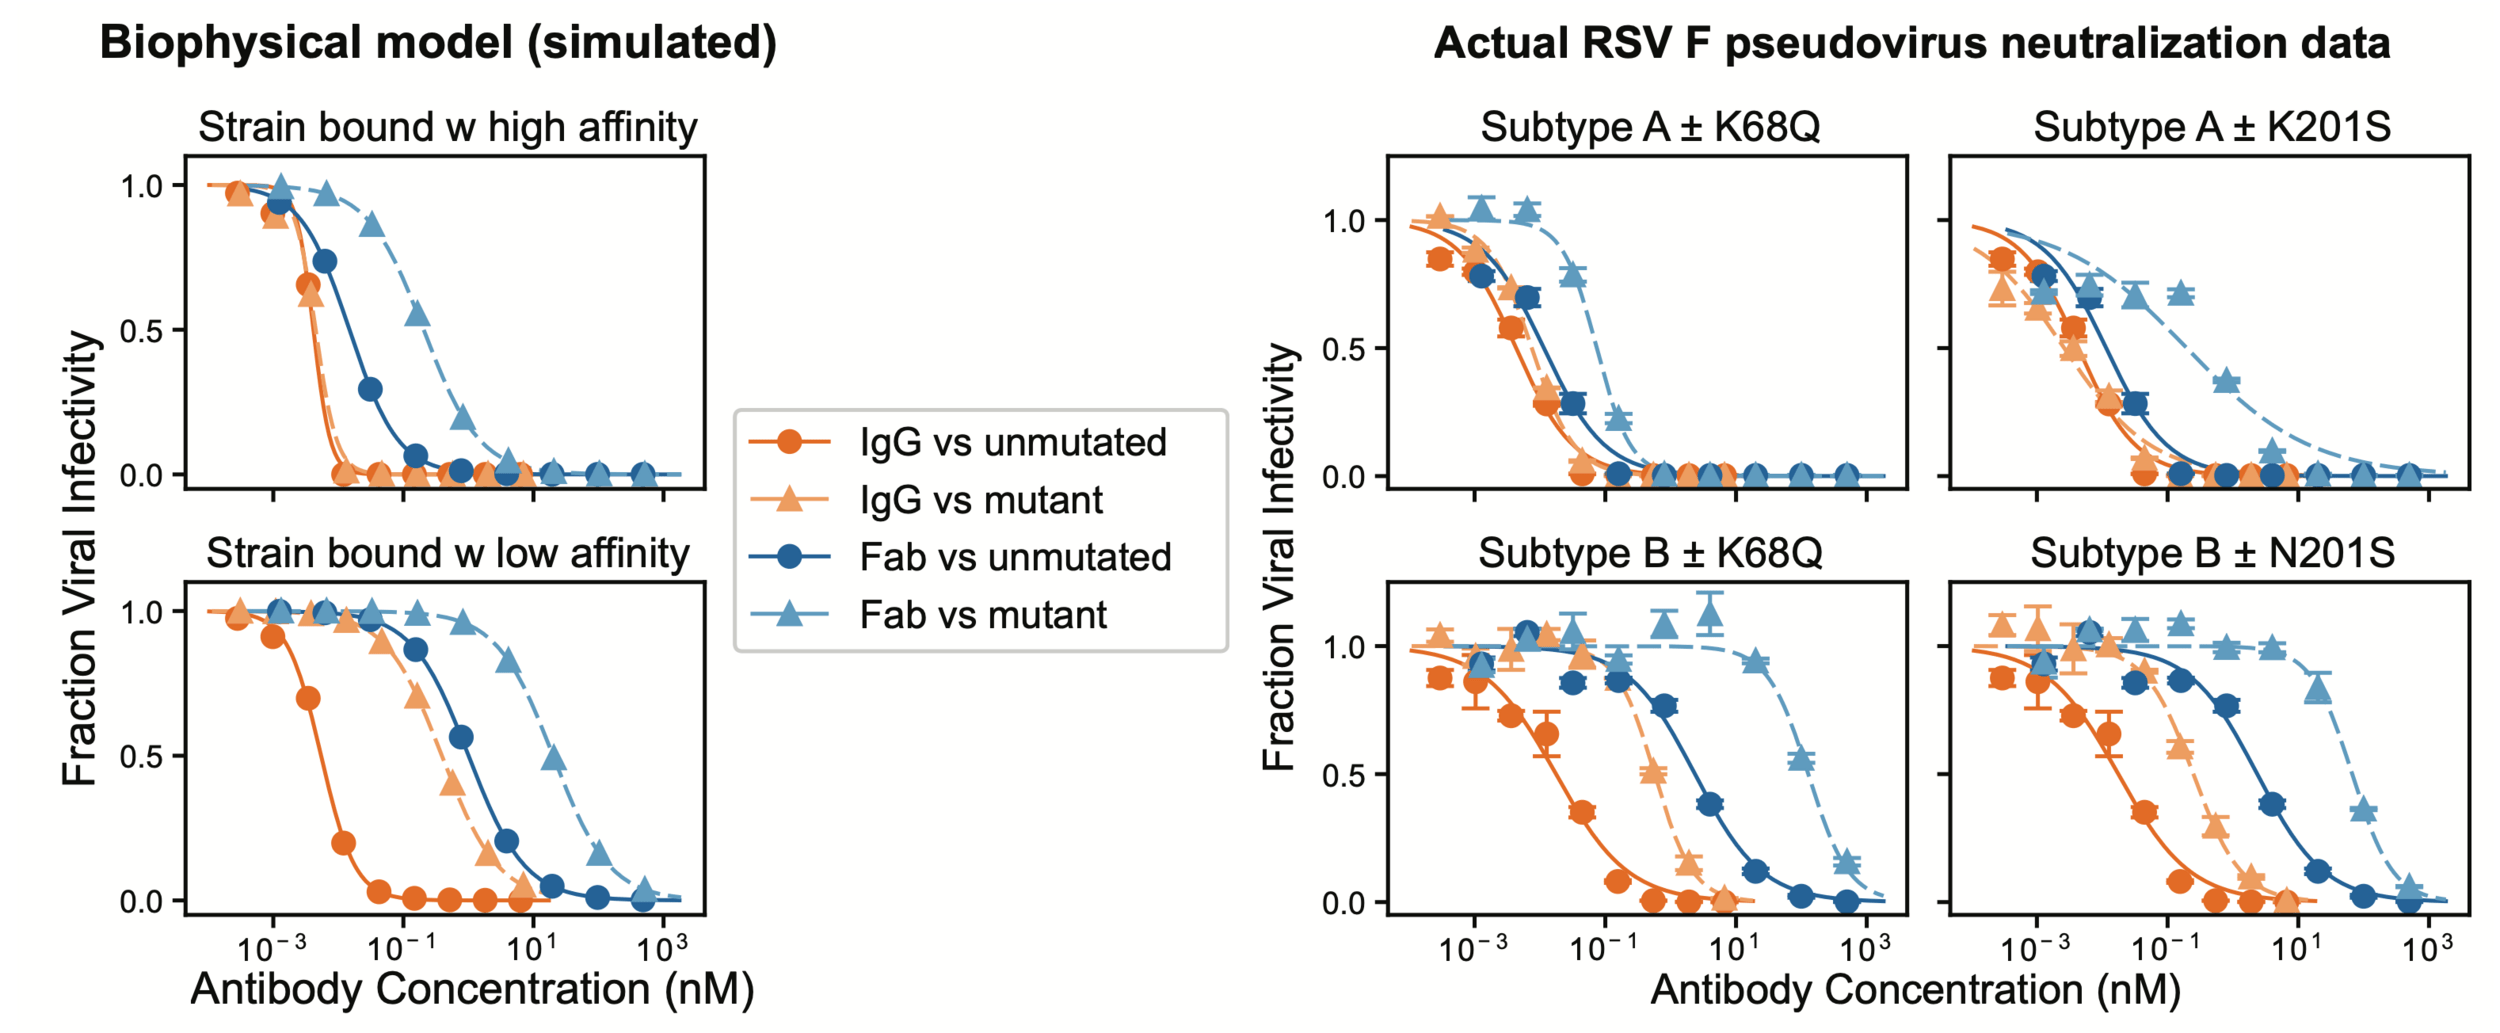
Biophysical model: IgG neutralization buffered against viral mutations when Fab potency high
See https://jbloomlab.github.io/IgG-vs-Fab-neutralization/notebook.html for full mathematical model
In real data, Fab potency higher to subtype A, thereby buffering IgG neutralization to mutations
Measurement of mutation effects to inform surveillance for RSV antibody resistance
Previously, resistance mutations identified by viral passaging and characterizing clinical isolates
Example studies serial passaging RSV in presence of antibodies:
Example studies identifying resistance mutations in clinical infections:
These approaches identify just a fraction of mutations that affect antibody neutralization, and do not distinguish causal and hitchhiking mutations.
We used deep mutational scanning to quantify how all F mutations affect neutralization
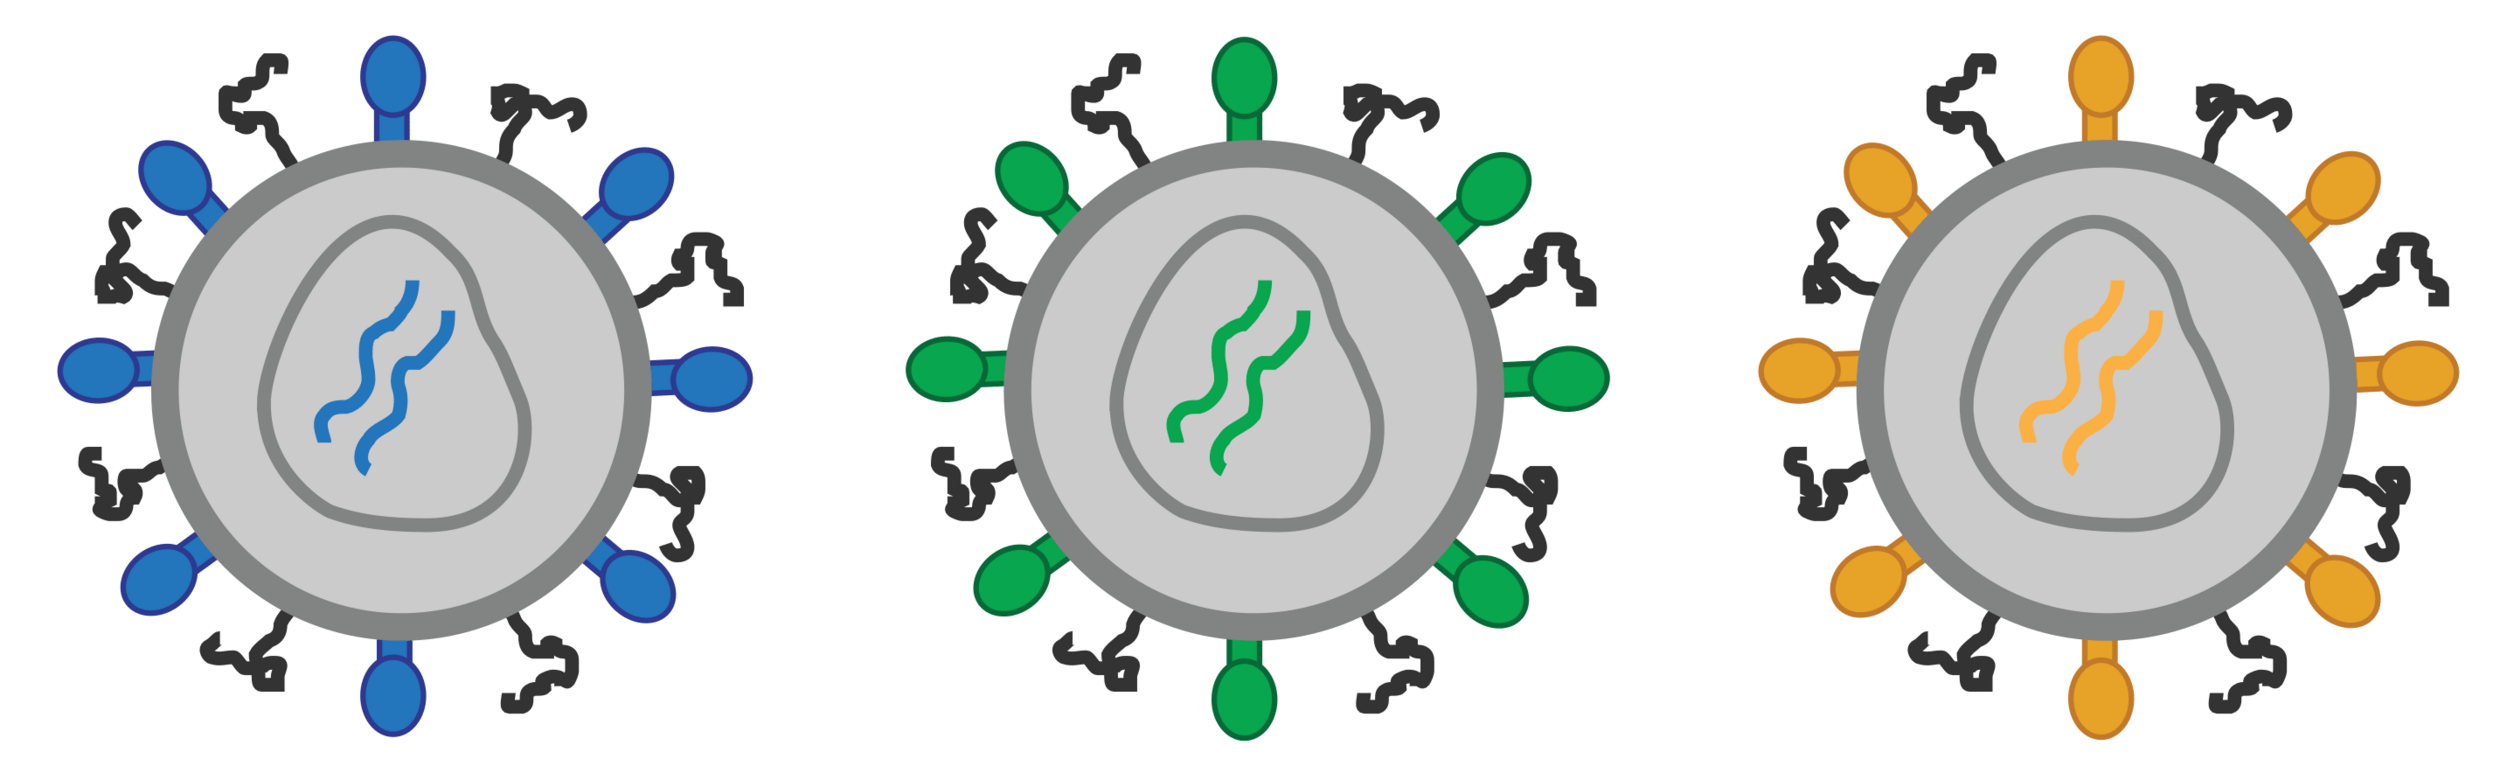
Library of pseudoviruses expressing all single amino-acid mutants of RSV F.
Pseudoviruses can only undergo single round of cell entry, and so provide safe way to study effect of F mutations.
To link genotype to phenotype, we encode entry protein in viral genome with barcode
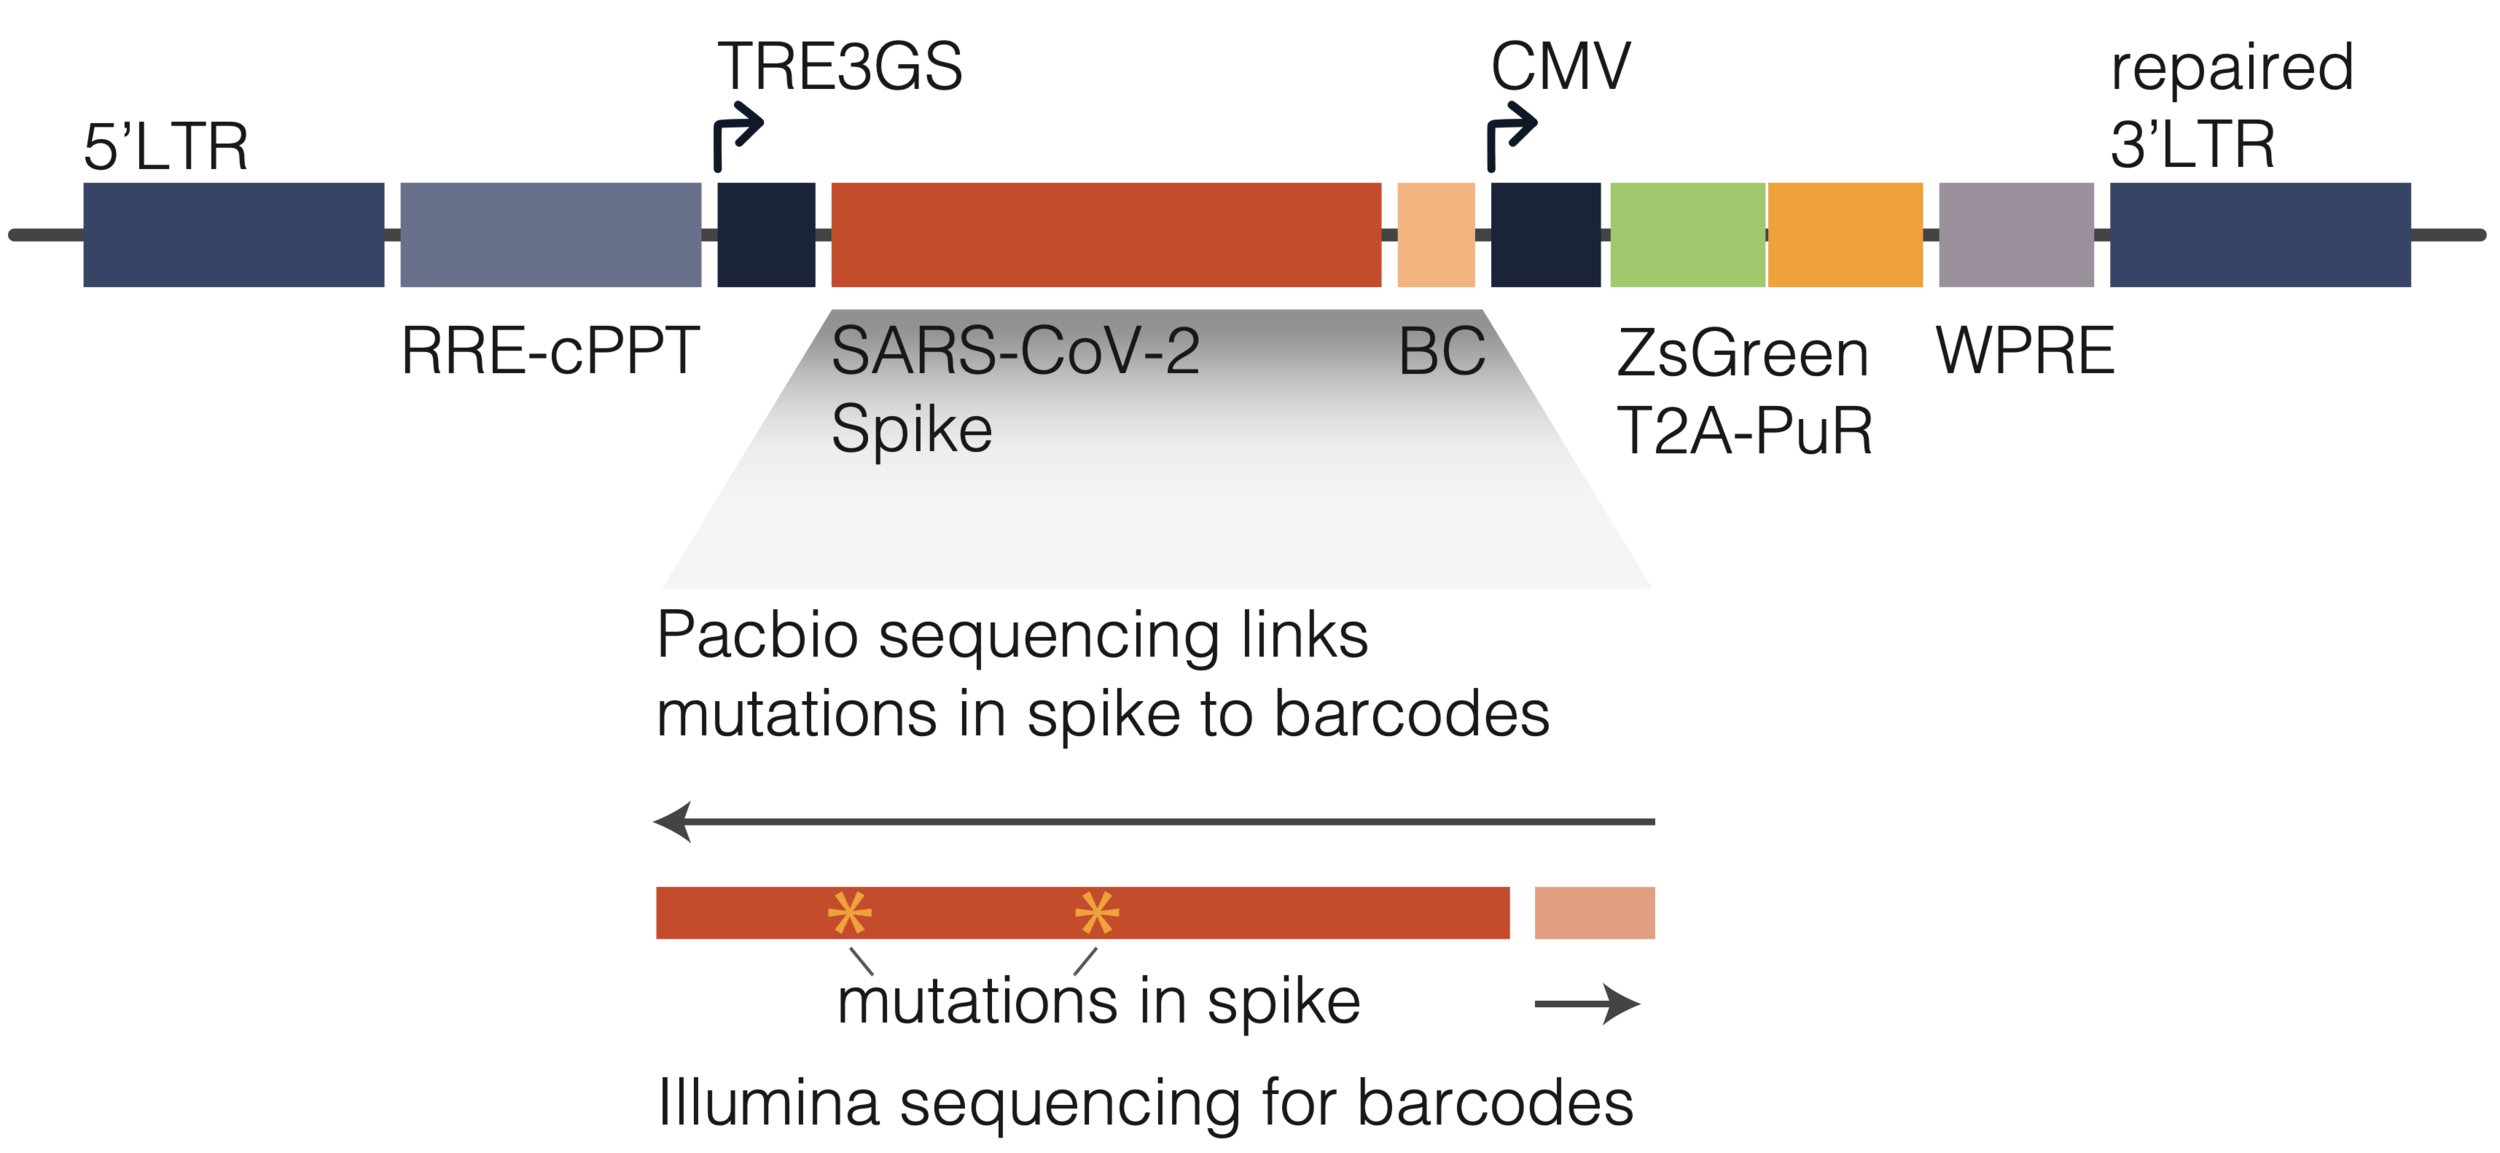
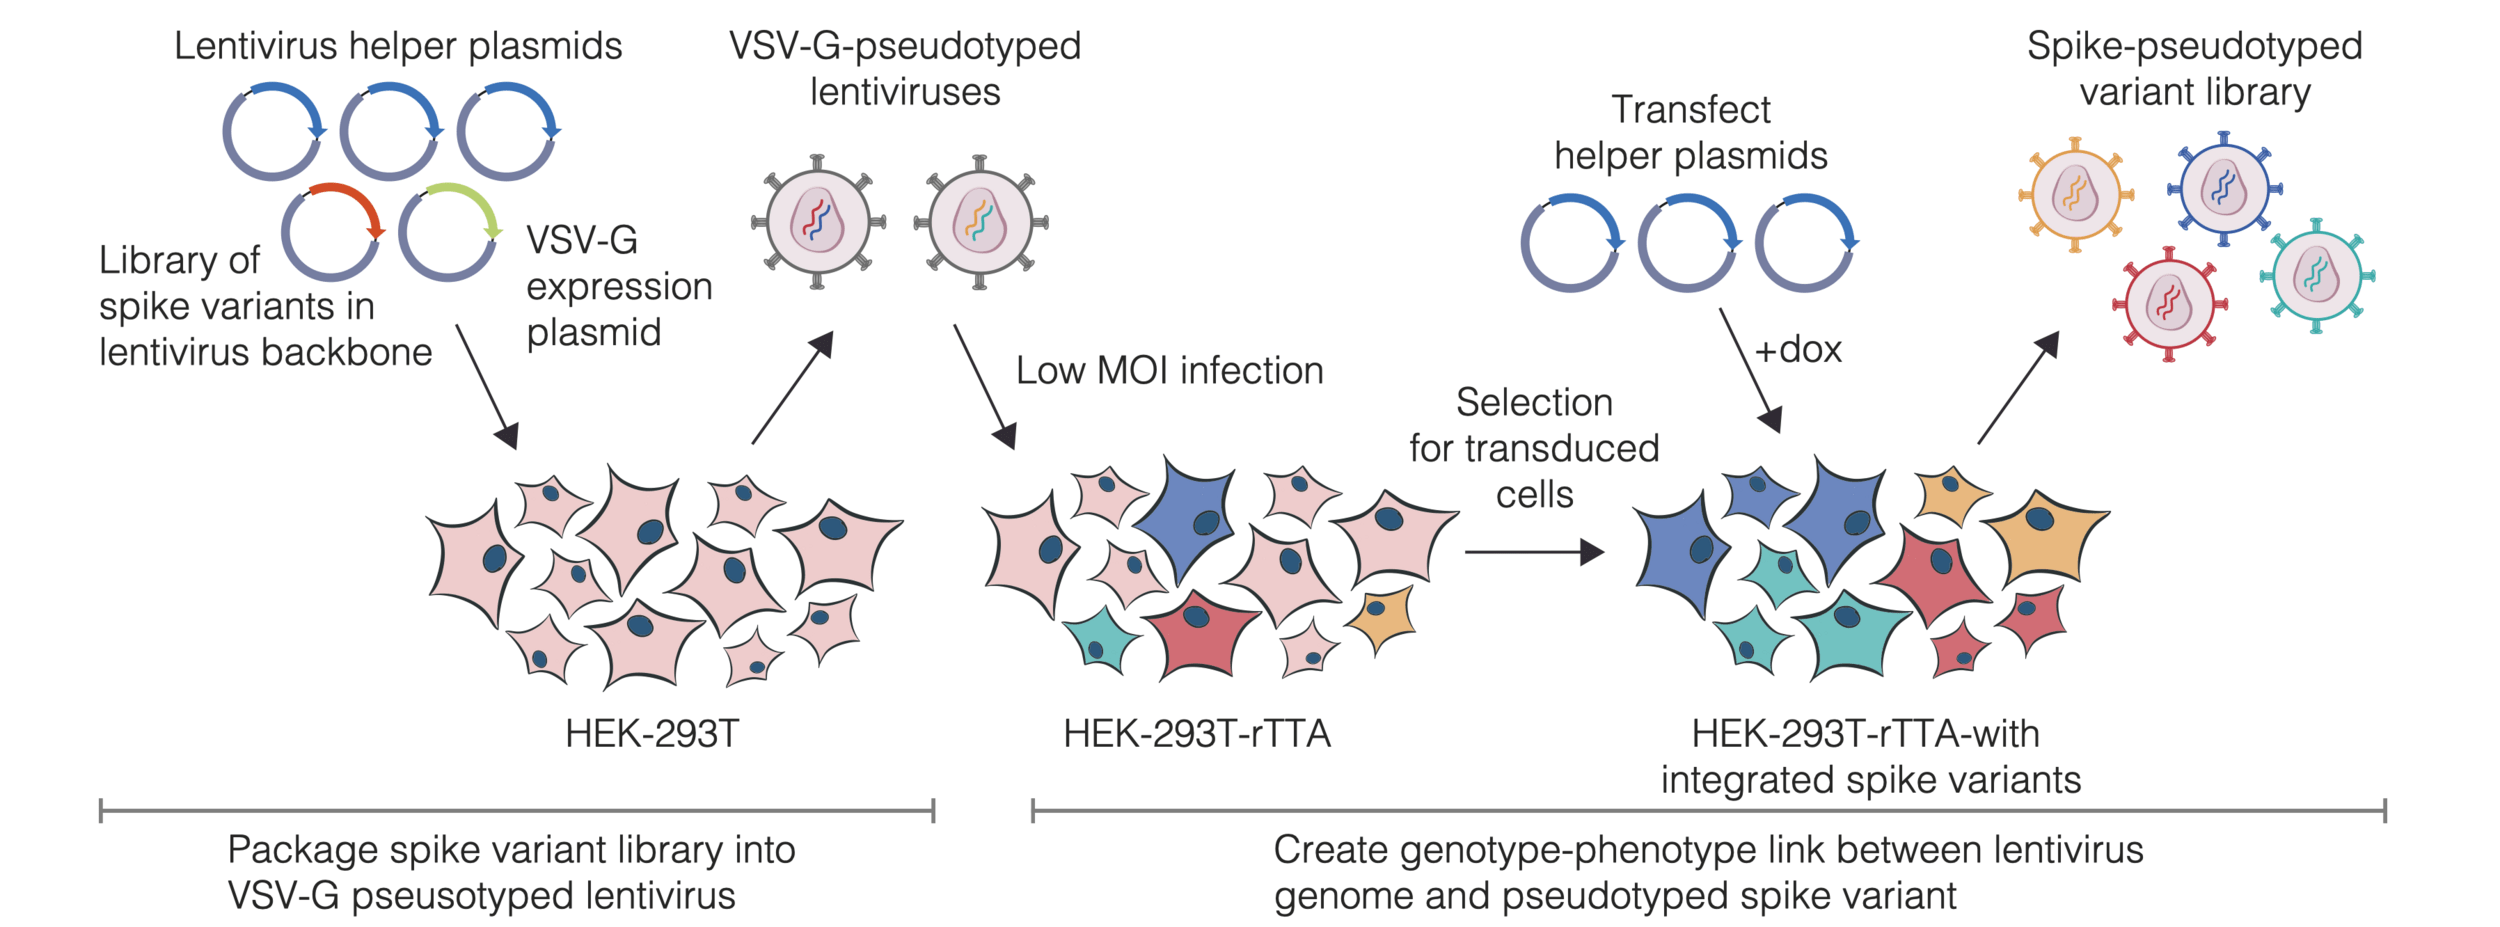
We then create genotype-phenotype linked libraries by two-step process
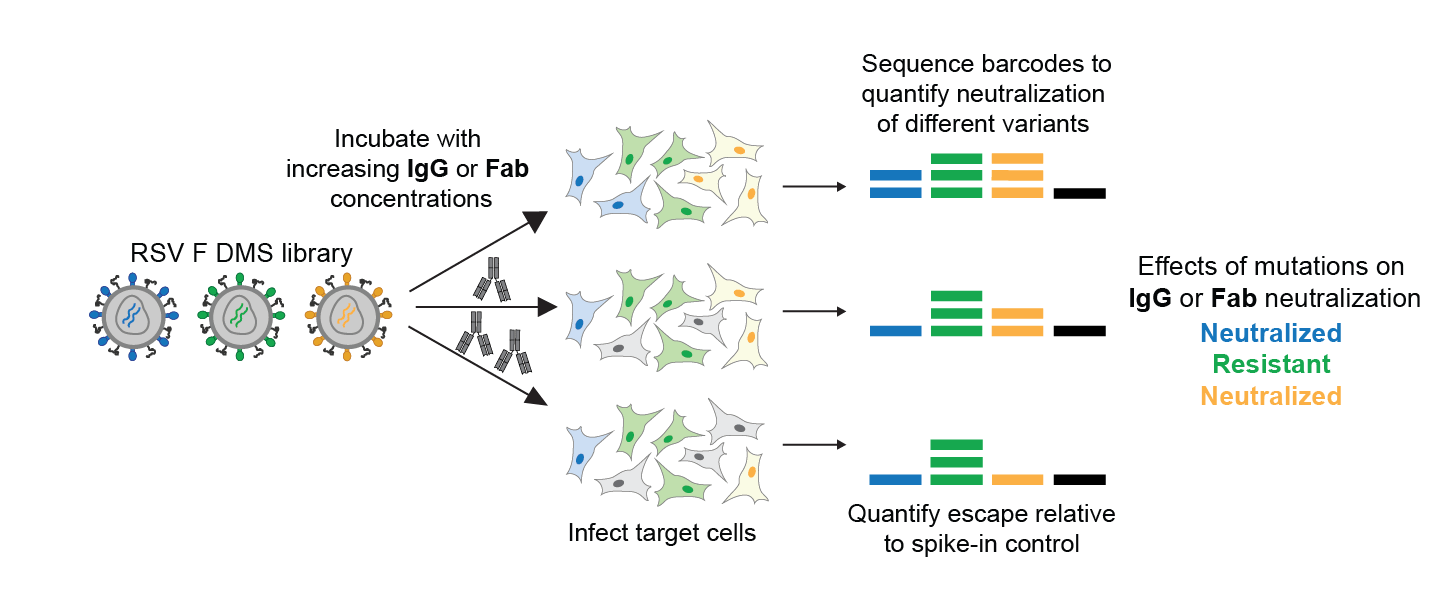
Workflow for measuring how all F mutations affect antibody neutralization
We can also measure how all mutations affect pseudovirus cell entry in absence of antibody, providing a measure of functional constraint.
How F mutations affect nirsevimab neutralization
We can compare functional tolerance for escape from different antibodies
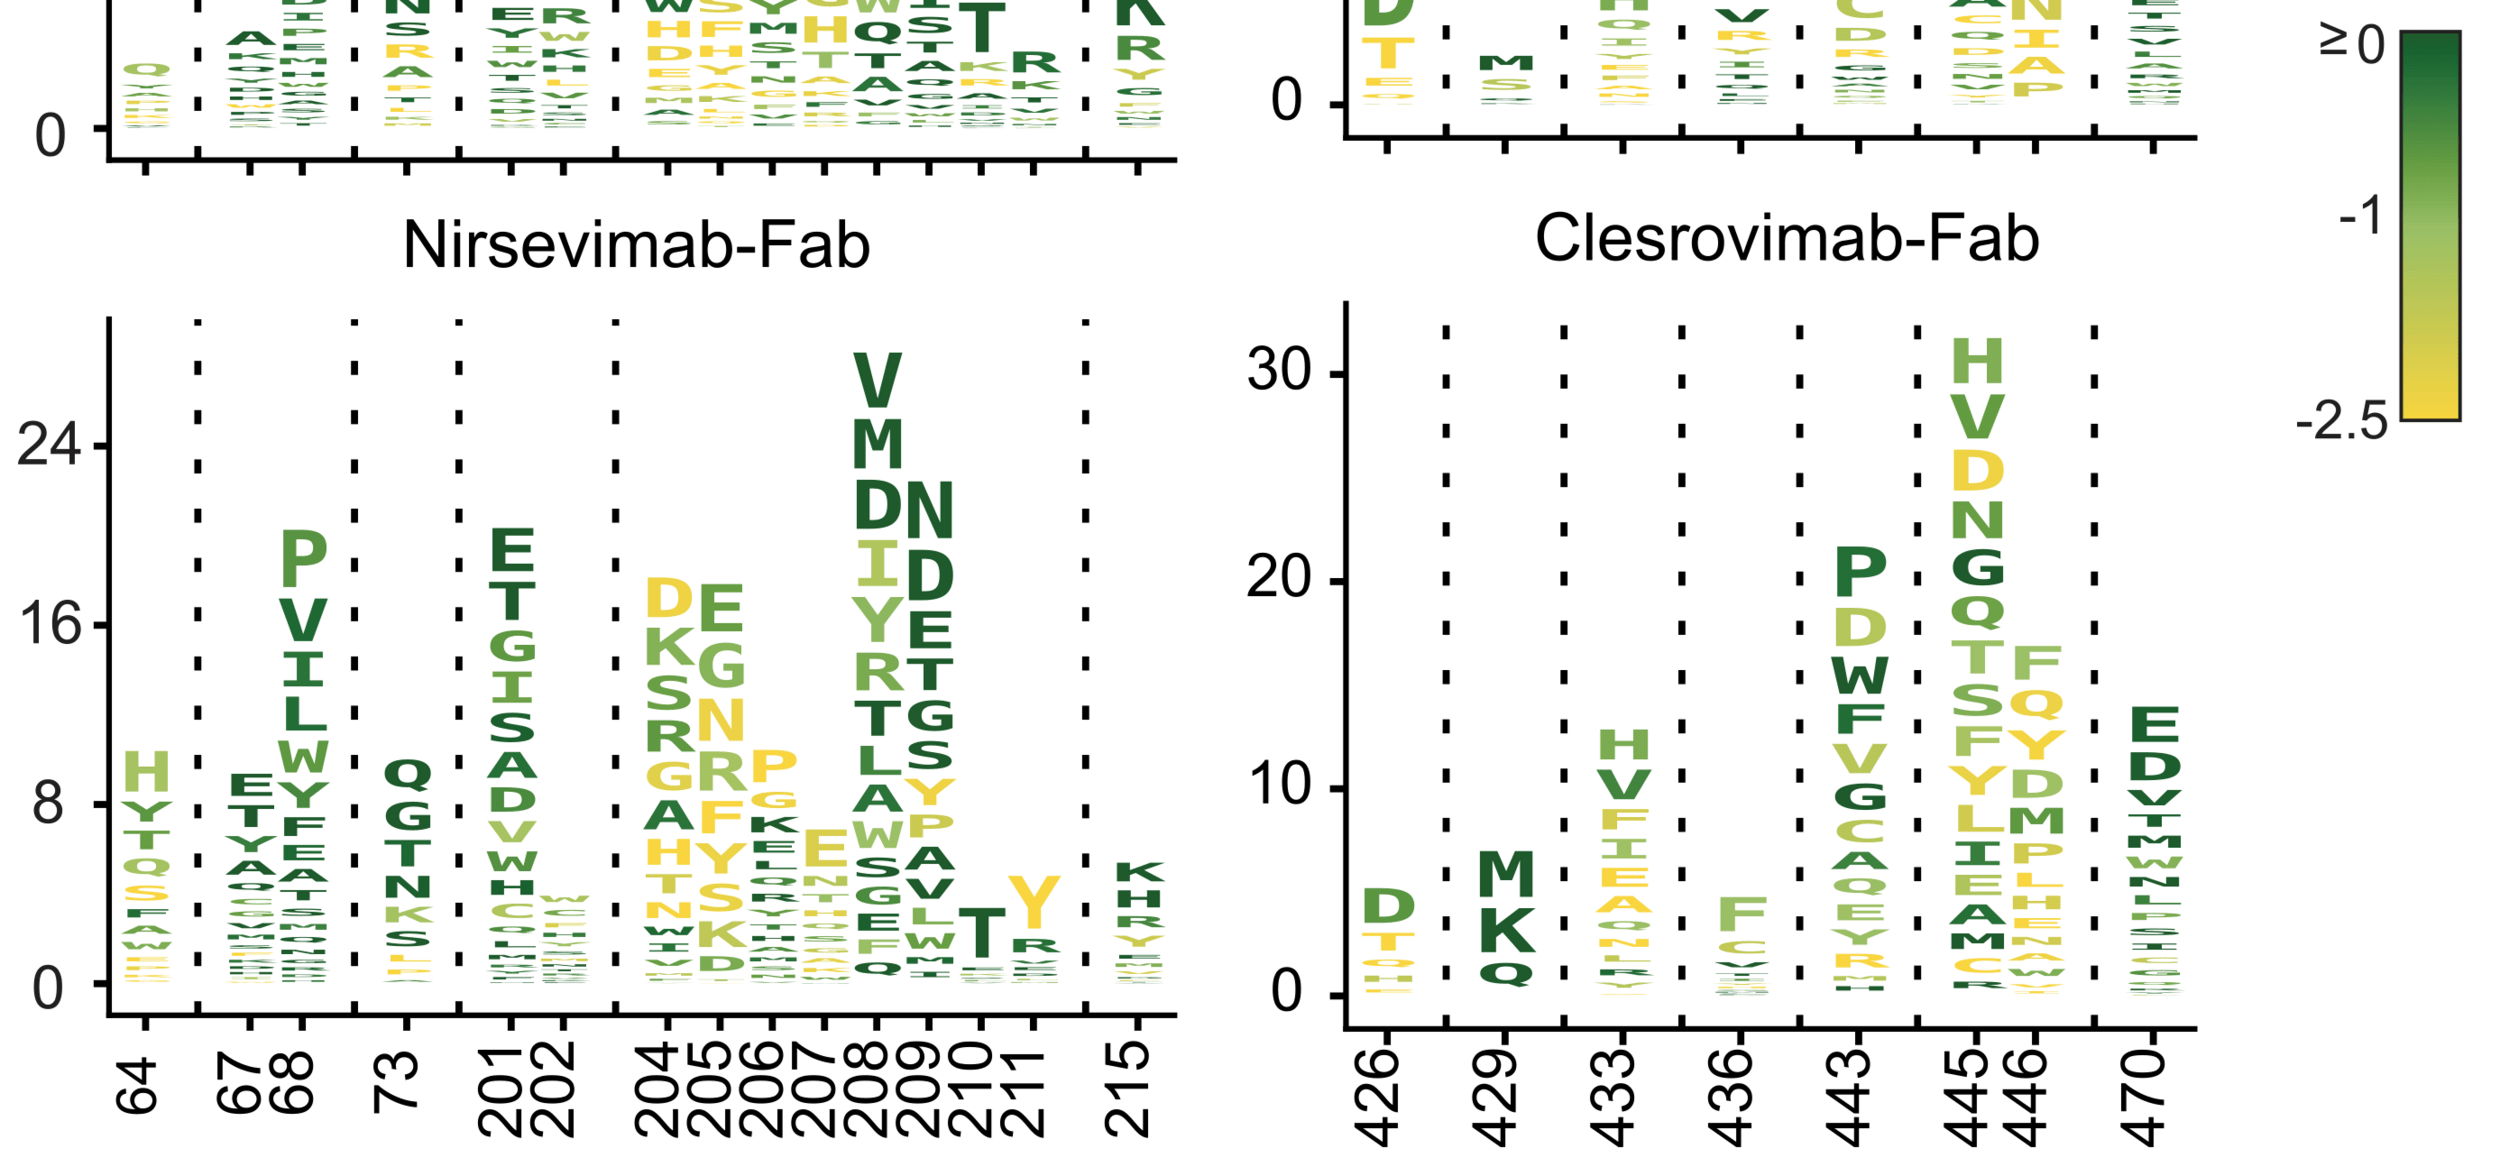
Letter heights indicate reduction in antibody neutralization, color indicates impact on F's cell entry function. These visualizations help quantify how constraint limits escape from different antibodies.
Nirsevimab
Clesrovimab
reduction in neutralization
site
cell entry function
Experimentally informed sequence surveillance
We can identify and validate natural strains with resistance
Conclusions
Difference in nirsevimab IgG resistance between RSV subtypes is explained by a biophysical model that accounts for different Fab potencies.
We have completely measured how RSV F mutations affect neutralization by antibodies in clinical use.
These data enable real-time surveillance for natural strains with resistance mutations.
We have applied similar pseudovirus deep mutational scanning to HIV Env, influenza HA, Nipah RBP and F, Lassa GPC, CHIKV envelope proteins
Thanks




Cassie Simonich
Pediatrics Medical Fellow
Seattle Childrens / Fred Hutch