Medicaid and Mortality: New Evidence From Linked Survey and Administrative Data
(by Miller, Wherry, and Johnson)
"Story of a paper" for BA 480
Professor of Business Economics and Public Policy at Ross

Ph.D. in Economics from University of Illinois in 2012




Post doctoral research at Michigan for RWJ Health Policy Scholars program

Assistant Prof. at Notre Dame Economics
Joined Ross in 2014!


What makes a good research idea?
A question that we want answered, that is answerable.
Lots of interesting questions that are not (currently) answerable-- "Why does the universe exist?"
Lots of uninteresting questions that are answerable--"What is the correlation between average rainfall and number of staplers sold in a county?"
Every paper starts with coming up with a good question to answer
Did expanding health insurance (Medicaid) through the Affordable Care Act reduce mortality?
What was the Affordable Care Act?
Back in 2010, then President Obama passed the Affordable Care Act -- a major and very controversial health care reform bill.
Main goal--expand health insurance coverage.
What was Coverage Like Before the ACA?
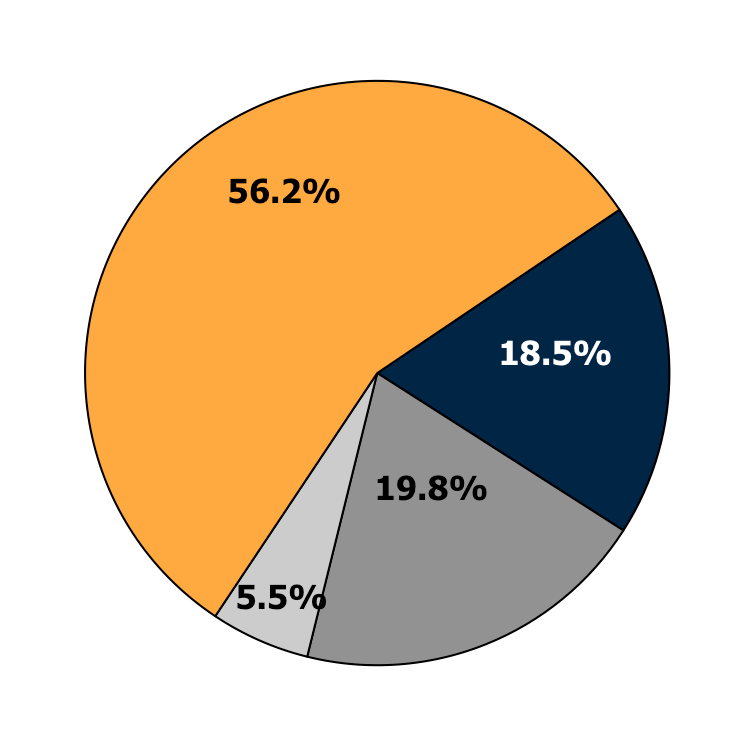
Employer-Sponsored
Health Insurance
Private Non-Group
Medicaid or other
public programs
Uninsured
Source: 2011 CPS ASEC, Non-Elderly Only
Declines in Coverage
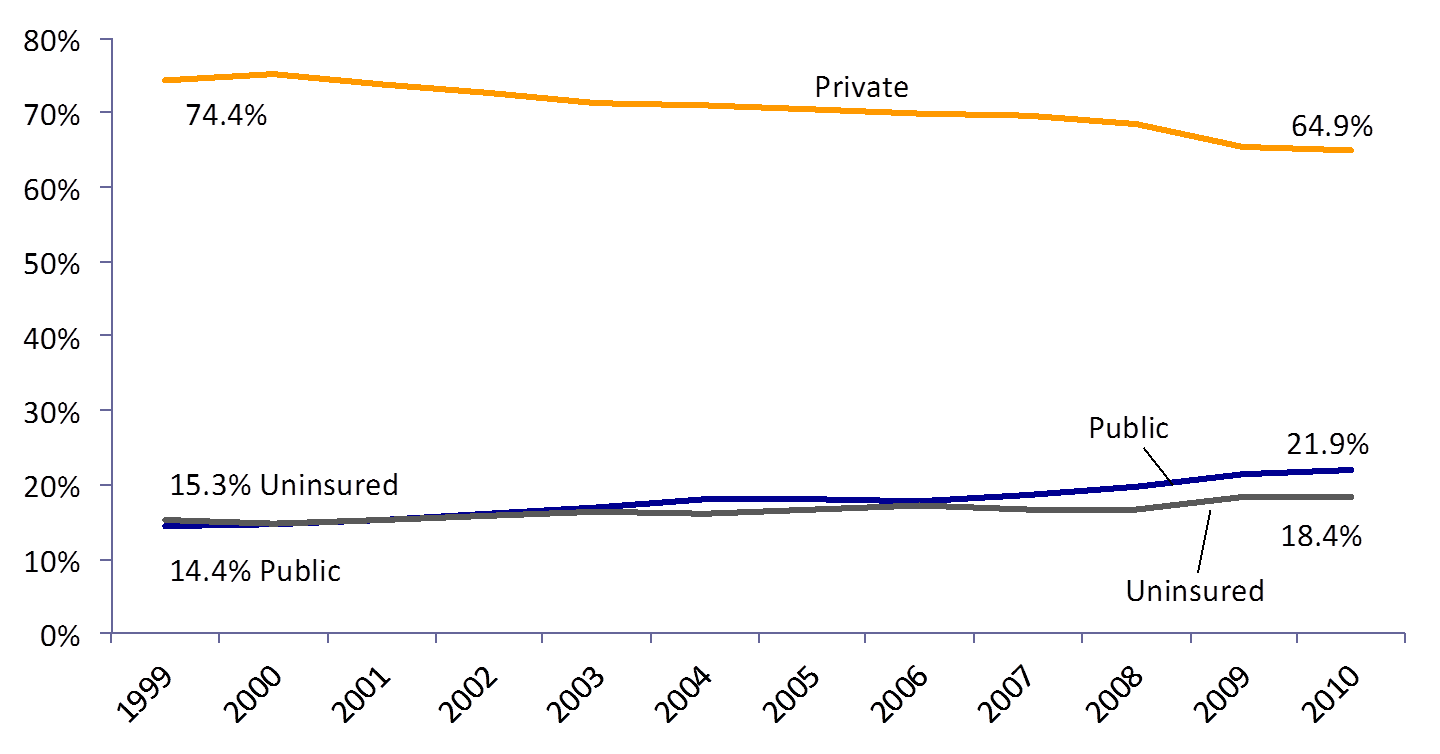
Source: DeNavas-Walt et al. Income, Poverty and Health Insurance Coverage in the United States: 2011, US Census Bureau (2012)
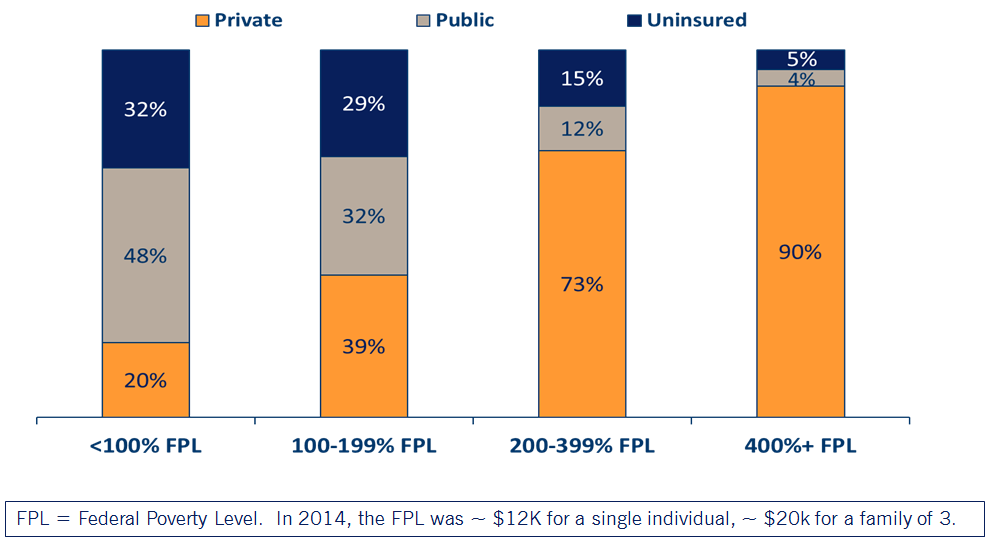
Health Insurance by Income Level
ACA Expanded Coverage in 3 Ways
1.Young adults allowed to stay on their parents’ private insurance until age 26 (effective September 2010)
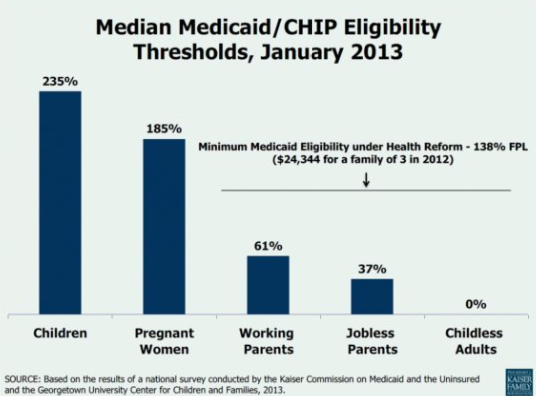
2.Eligibility for Medicaid extended to everyone with incomes below 138% of the Federal Poverty Level (effective Jan 2014*)
3.New tax credits for private insurance for families between 100 and 400% of the Federal Poverty Level (effective Jan 2014)
* Several states elected to expand Medicaid at different times, or not at all!
Medicaid Expansion
Why is this interesting?
We didn't know the answer - on the policy side.


Why is this interesting?
We didn't know the answer - on the policy side.


Just analyzing overall mortality rate -- including many people not affected by the Medicaid expansion -- would not work.
Power analyses: current datasets insufficient
- Large randomized controlled trial that assigned Medicaid eligibility
- Highly credible design
- Effects on mortality were inconclusive
Oregon Health Insurance Experiment

On the research side...
- Can't just compare people who sign up vs who don't
- If everyone gains eligibility, who is the comparison group?
Need some variation in who expands Medicaid
On the research side...

- We don't really know if insurance improves health
- The uninsured get a lot of care--maybe they are able to get all the care they need
- Even if we see improvements in a small experiment, do we know if those will translate to broader populations?
Overall conclusion?
On the research side...

How to overcome these challenges to answer the research question?
Medicaid Expansion
How did the government plan to expand Medicaid?
- Federal match assistance percentage (FMAP): States were historically guaranteed at least a 1-to-1 match from federal government.
- Higher match rate for lower income states (highest is MS, 2.8 to 1 in 2015)
- Under ACA, federal government pays 100% of additional costs during 2014-2016, then phases down to 90% by 2020.
- Under the original law, states have to expand Medicaid or risk losing all of their funding
NFIB v Sibelius 2012
High profile supreme court case challenging constitutionality of the ACA:
SCOTUS ruled the threat of losing all Medicaid funding was unconstitutionally coercive, a "gun to the head" as Roberts wrote in his majority opinion.
Because of this ruling, states could opt not to expand Medicaid without risking losing additional funding.
This created a natural experiment where some states adopted eligibility expansions and some didn't.
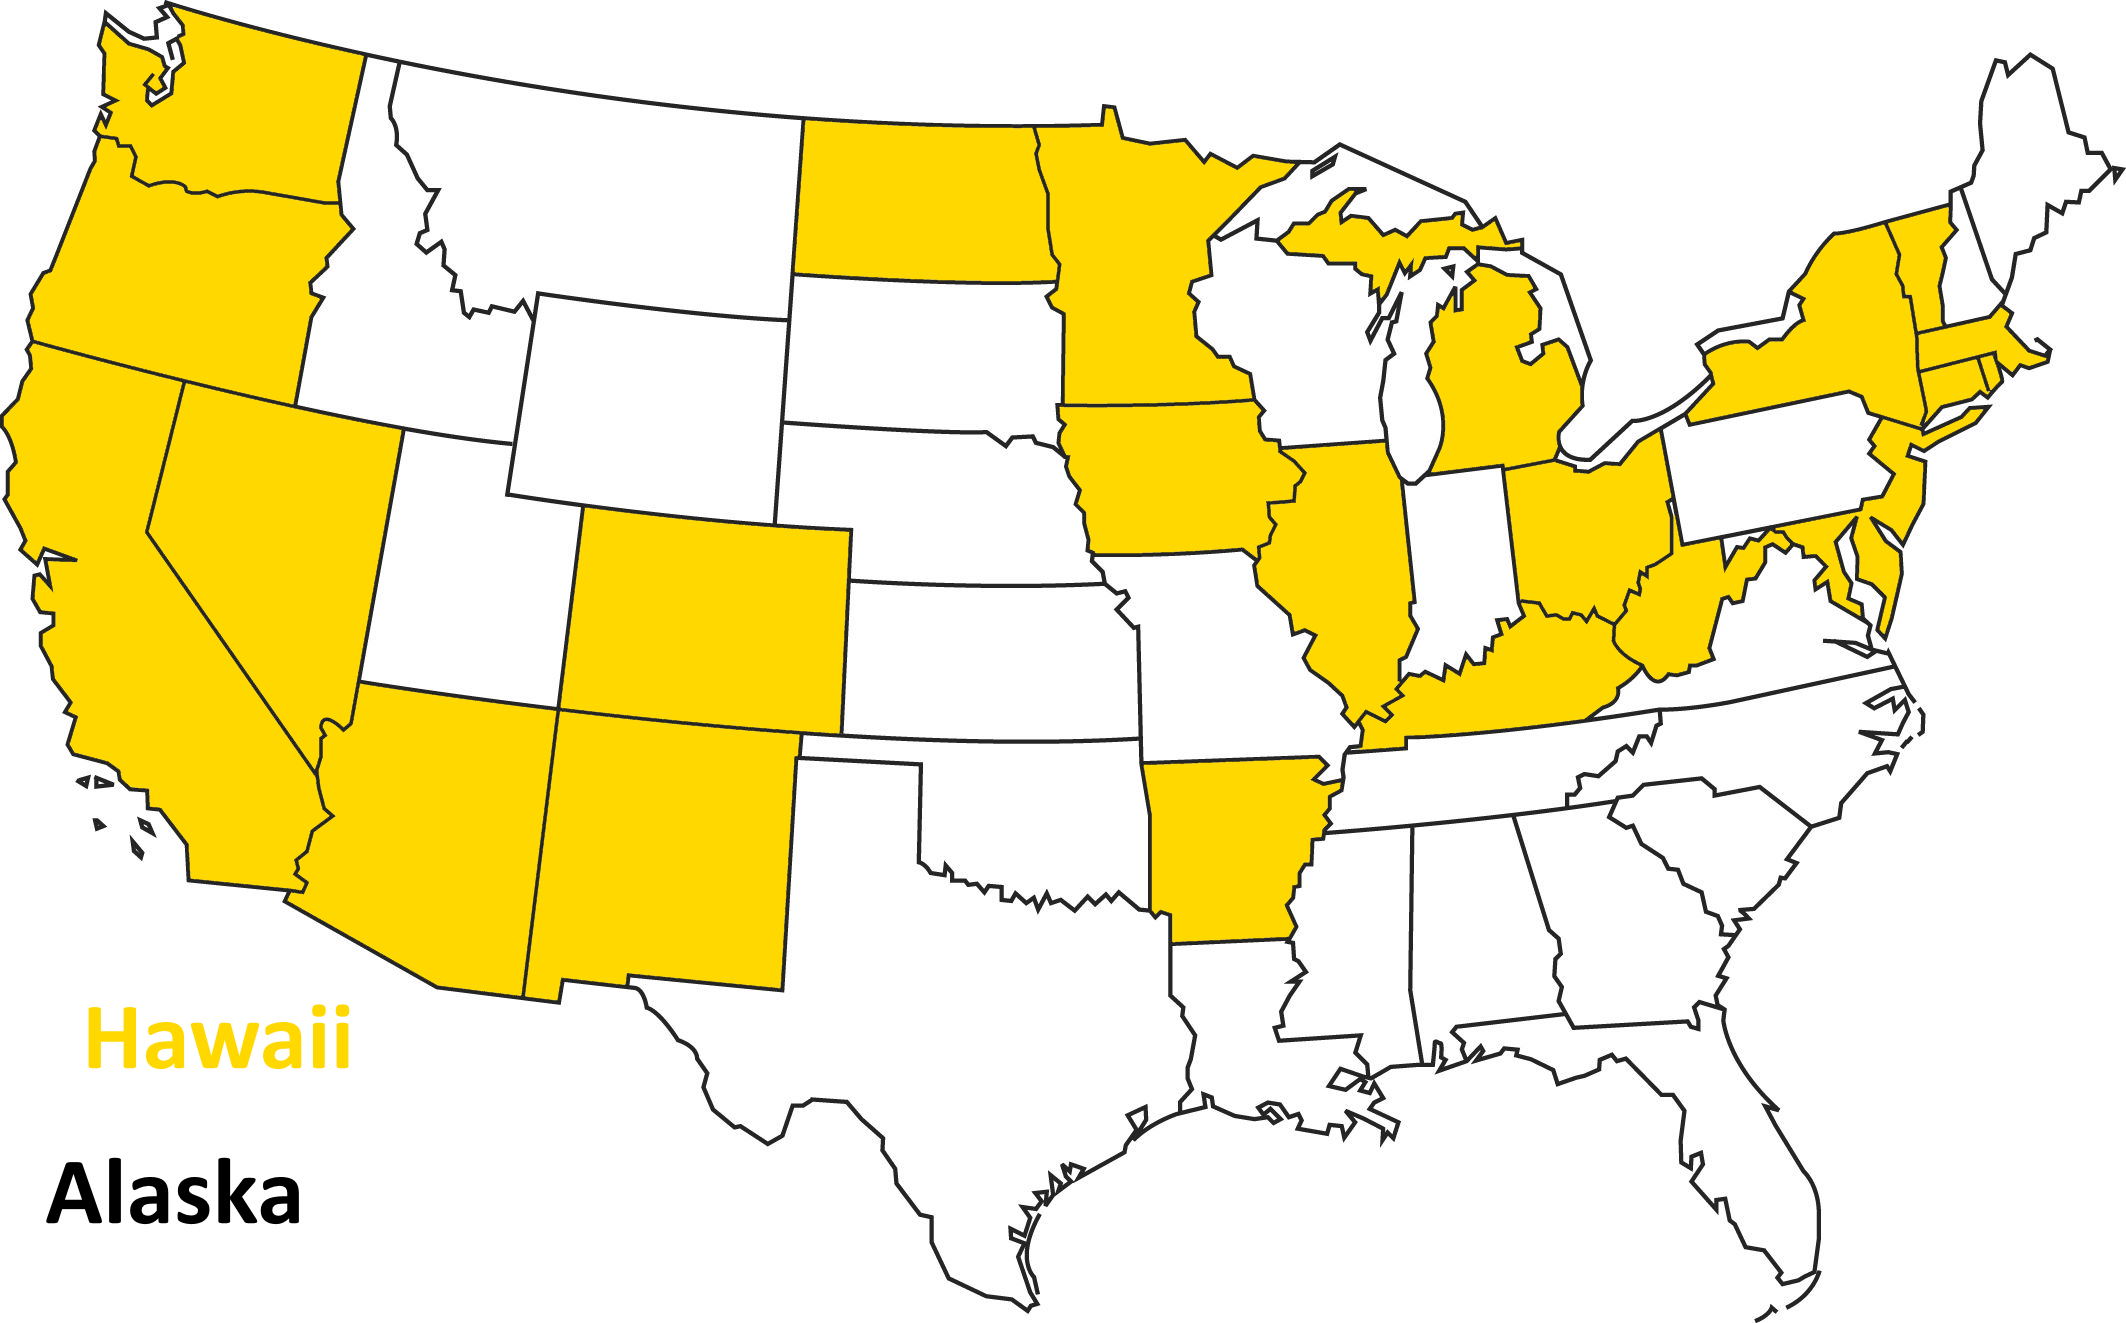
Opted to Expand in 2014
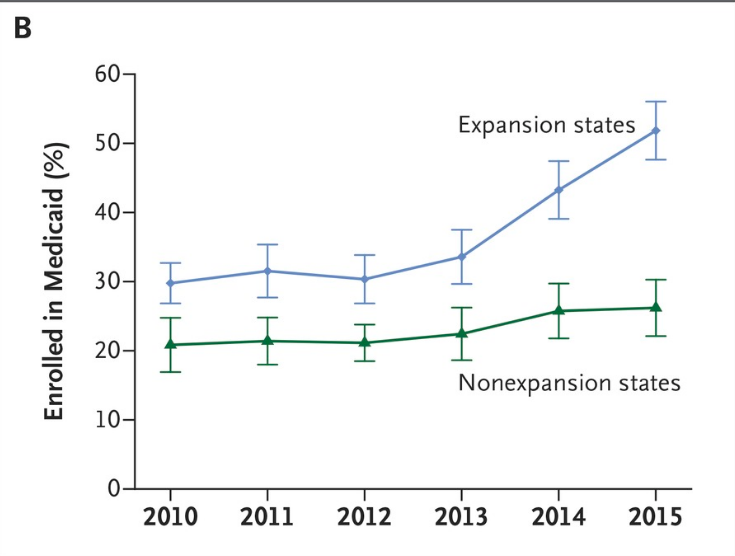
Coverage Gains Largest in states that expanded Medicaid
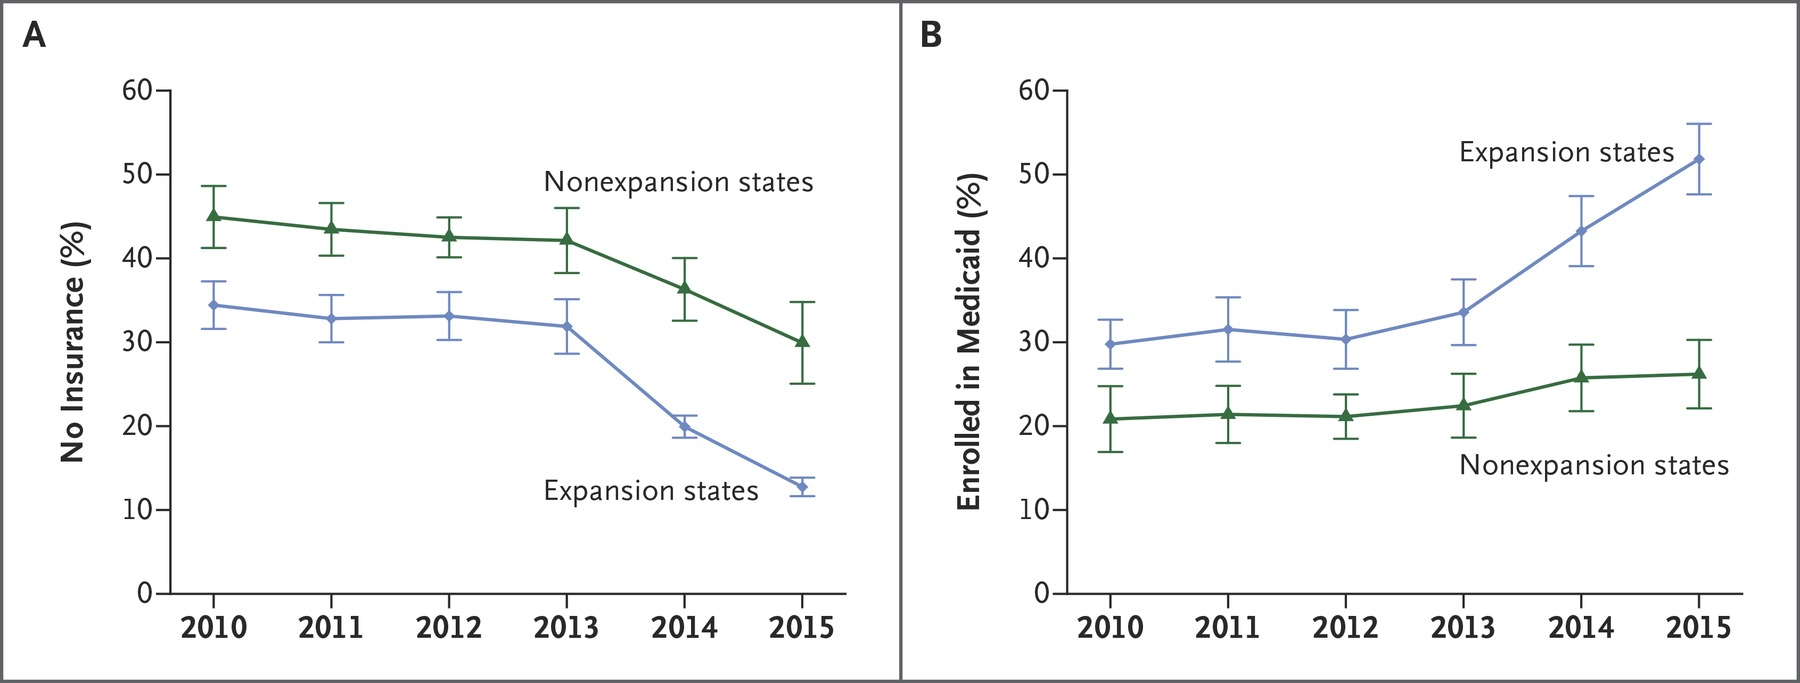
Sample among low income adults, Miller and Wherry 2016 New England Journal of Medicine
Analysis of ACA Medicaid Expansions
- Take advantage of non-universal adoption of the Medicaid expansion that resulted from the 2012 Supreme Court decision.
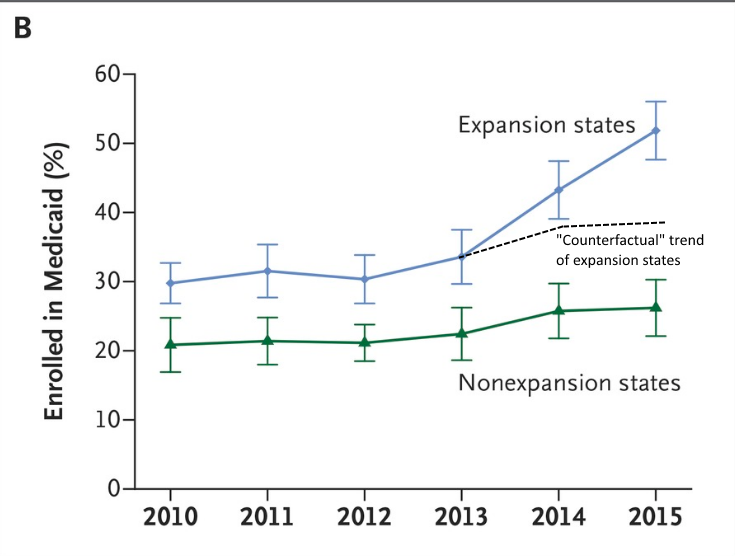
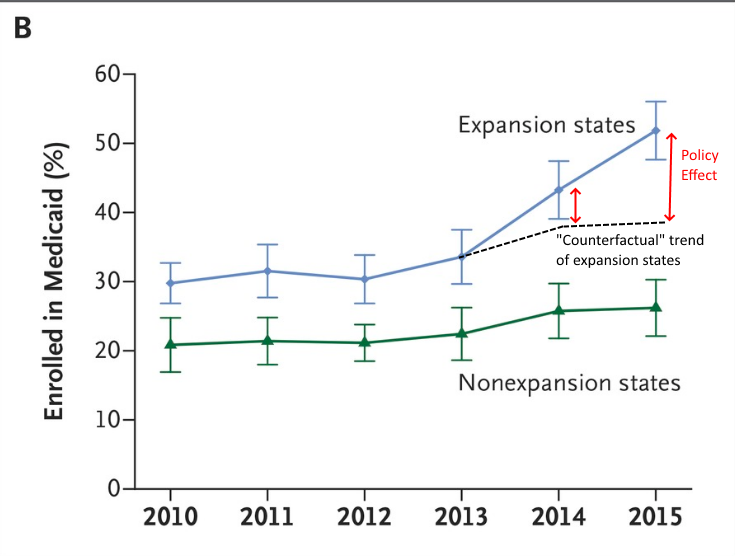
- Use a "difference in differences" quasi-experimental empirical design
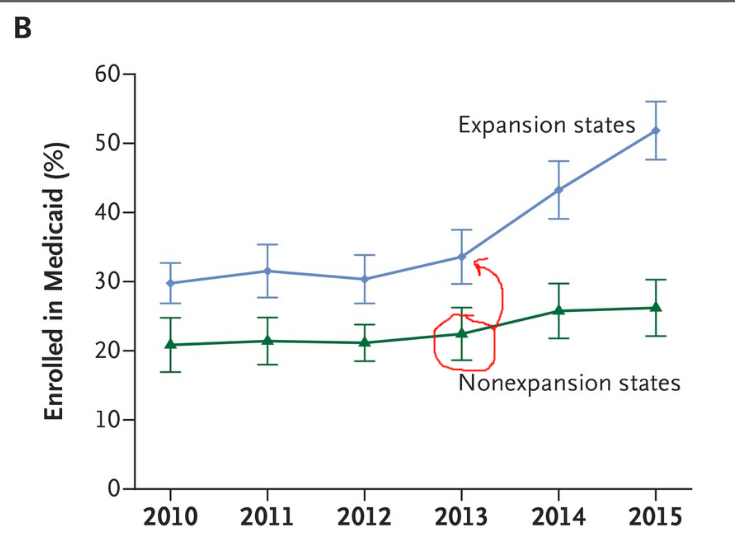
Compare changes in outcomes across expansion and non-expansion states.
Expansion states and non-expansion states might be at different levels, but are they on the same trajectory?
Difference in Differences
Let's go back to this figure:
Difference in Differences
Let's go back to this figure:
Difference in Differences
Let's go back to this figure:
Difference in Differences
Let's go back to this figure:
Difference in Differences
One way to represent this would be to subtract out the difference in one year (normalize to zero) and then plot the remaining difference.
Difference in Differences
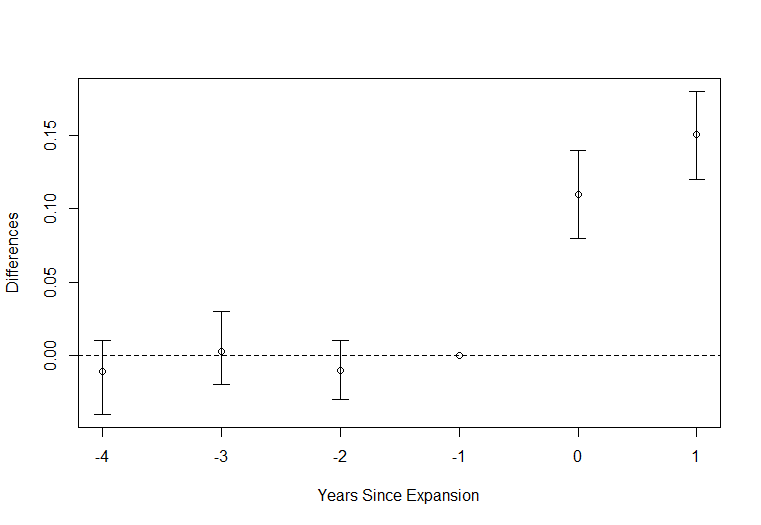
Data Challenge
Typically data on mortality does not contain information on socio-economic characteristics such as income or insurance coverage.
- Makes it difficult to analyze mortality impact of Medicaid because you don't know who would actually be eligible.
Mortality is not a very common outcome for the non-elderly (elderly are covered by Medicare already so not relevant).
- You need a really big sample to have enough statistical power.
Data Solution
Solution for this paper: link data from American Community Survey (ACS) to Social Security Administration mortality records
- ACS is large survey (4 to 4.5 million respondents per year) and has information on household income, eligibility for other programs, and other information relevant to determine who is most likely to gain eligibility
- We focus on individuals age 55-64, low income or disadvantaged (no high school degree), not otherwise Medicaid eligible, citizens.
- A large % of this group gained Medicaid eligibility.
- Follow this group across expansion and non-expansion states for 4 years after the ACA expansions.
How Many Gained Eligibility?
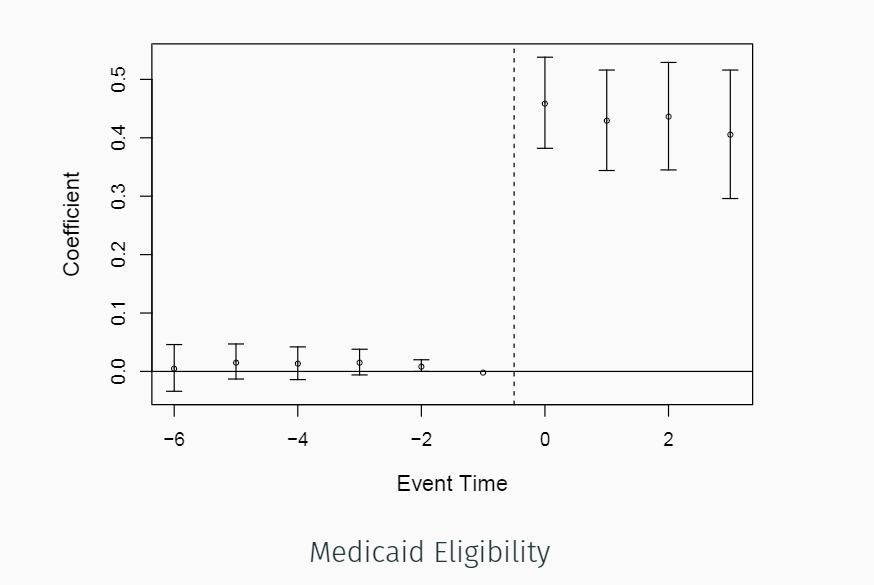
Nearly half of the group gained eligibility
How Many Gained Eligibility?
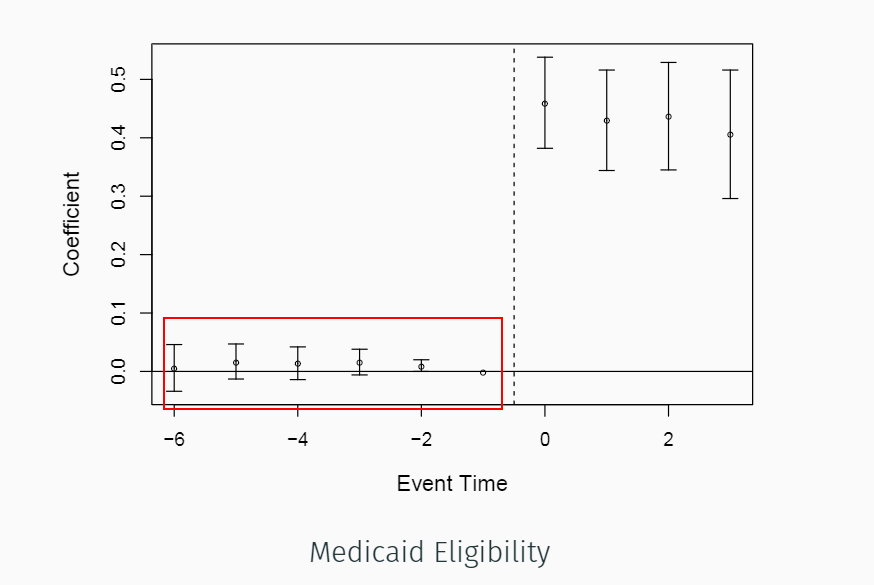
Notice! What does this tell us?
How Many Enrolled?
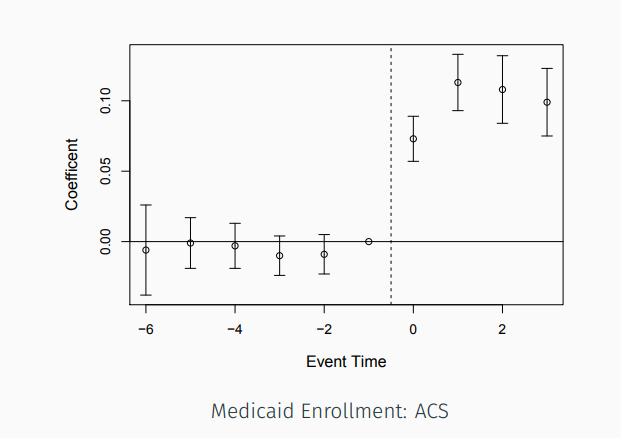
About 10-11percent enrolled, possibly higher due to misreporting in survey
Takeaway?
In the paper, we show this for other measures and other surveys (NHIS) as well.
- Successfully identified a group that was highly impacted by Medicaid expansions.
- ACA policy had meaningful impact on coverage for this group.
Mortality
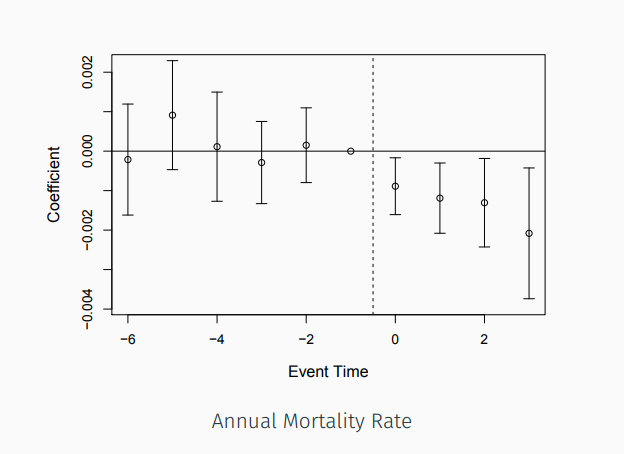
Probability of mortality for all who were alive at the beginning of the year
Mortality
Reduction of 0.09 percentage points first year, increasing to about 0.2 percentage points by year 4
Other Results
- Younger ages: Much smaller effect that is not statistically significant
- By cause of death: cardiovascular disease and diabetes are the biggest drivers
- No effect on "external" causes like opioid overdoses, suicides, and murders--seems to be driven by disease related deaths.
Question answered!

Debates continue but with new evidence...



Medicaid is always a program in the news!

Some tips!
Follow your curiosity
Keep your expectations manageable
Think hard about correlation vs causation
What questions do you have?